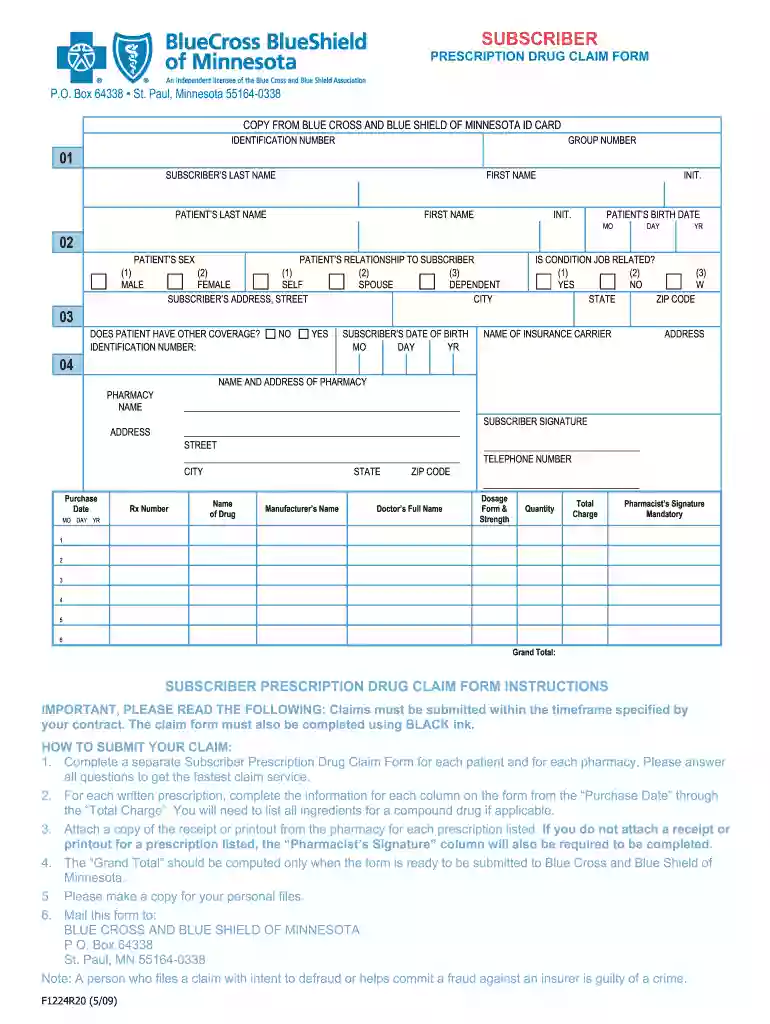
blue cross blue shield reimbursement form Preview on Page 1

Mn bcbs claim form 2026

Here's how it works

  • 01. Edit your blue cross blue shield reimbursement form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.

  • 03. Share your form with others

    Send bcbs reimbursement form via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out mn bcbs claim form with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the mn bcbs claim form in the editor.
  2. Begin by entering your identification number and group number at the top of the form. This information is crucial for processing your claim.
  3. Fill in the subscriber's last name, first name, and address details. Ensure accuracy to avoid delays.
  4. Provide patient information including their last name, first name, birth date, and sex. Indicate the patient's relationship to the subscriber.
  5. Answer whether the condition is job-related and if the patient has other coverage. If yes, include details about the other insurance carrier.
  6. List pharmacy details including name and address. Then, complete each column for prescriptions from purchase date to total charge.
  7. Attach receipts or printouts from the pharmacy for each prescription listed. If not available, ensure pharmacist’s signature is provided.
  8. Calculate and enter the grand total before submitting your claim.

Start using our platform today for free to streamline your mn bcbs claim form submission!

See more blue cross blue shield reimbursement form versions

We've got more versions of the blue cross blue shield reimbursement form form. Select the right blue cross blue shield reimbursement form version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20094.9 Satisfied (484 Votes)

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

Related links

MEDICAL BENEFITS SUBSCRIBER CLAIM FORM

SUBSCRIBER CLAIM FORM. Mail completed form and all required information to: P.O. Box 21146. Eagan, MN 55121-0146. Please Note-If a participating providerRead more

Learn more
Health Benefits Claim Form - CareFirst BlueCross BlueShield

I request benefits for these expenses and DocHub that the above information is correct and that the foregoing expenses were incurred for the above.

Learn more
Electronic claim attachments - MN.gov

Follow these steps: Enter the unique ACN (including spaces and hyphens) on each attachment page, the cover sheet and your electronic claim.Read more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here