




Here's how it works
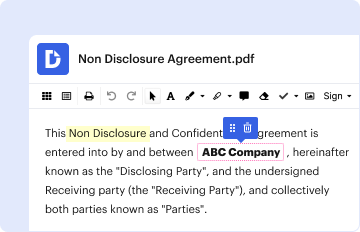
01. Edit your 2870 form online
Type text, add images, blackout confidential details, add comments, highlights and more.
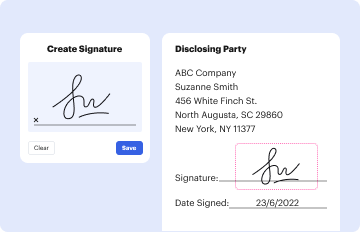
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
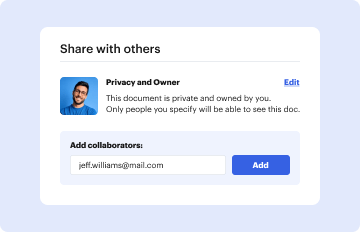
03. Share your form with others
Send dd 2870 via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out dd 2870 example with our platform

- Click ‘Get Form’ to open the dd 2870 example in the editor.
- Begin by entering your personal information in the designated fields, including your name, address, and contact details. Ensure accuracy for effective processing.
- Next, navigate to the section regarding your eligibility. Carefully read each statement and select the appropriate options that apply to your situation.
- In the signature section, use our platform’s tools to add your digital signature. This step is crucial for validating your submission.
- Finally, review all entered information for completeness and correctness before saving or submitting the form directly from our editor.
Start using our platform today to fill out your dd 2870 example easily and for free!
Fill out dd 2870 example online
It's free
It's free
Got questions?
We have answers to the most popular questions from our customers. If you can't find an answer to your question, please contact us.
Contact us
What is dd form 2870 used for?
AUTHORITY: Public Law 104-191; E.O. 9397 (SSAN); DoD 6025.18-R. PRINCIPAL PURPOSE(S): This form is to provide the Military Treatment Facility/Dental Treatment Facility/TRICARE Health Plan with a means to request the use and/or disclosure of an individuals protected health information.
How do I fill out a release of information form?
Begin by specifying your name, the entity authorized to disclose information, and the individuals or entities you authorize to receive it. Indicate the specific information and purpose for which it will be disclosed, add an expiration date or event, and sign and date the form to confirm your consent.
What form do I need to request medical records for the Air Force?
You may request a copy of your recent medical records by accessing the DD FORM 2870, Authorization for Disclosure of Medical or Dental Information.
Where to submit dd form 2870?
Once patient completes the form, they will turn it in at the Medical Records Window at FAHC in person. 2. Fax the request to 256-842-0655 with a copy of your military ID or state drivers license. NO EXCEPTIONS.
What is the purpose of the authorization to release information?
A consent to release medical information form will typically be requested when someone wants a copy of their own medical records or would like to have them sent to a third party. The request is made to the healthcare provider, therapist, or organization that has the patients records.
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


People also ask
What is a 2870?
Authorization for Disclosure of Medical or Dental Information (DD Form 2870) Your provider or contractor will use this form to get your permission to share your protected health information to a third party for personal use; insurance; continued medical care; school; legal; retirement or separation; or other reasons.