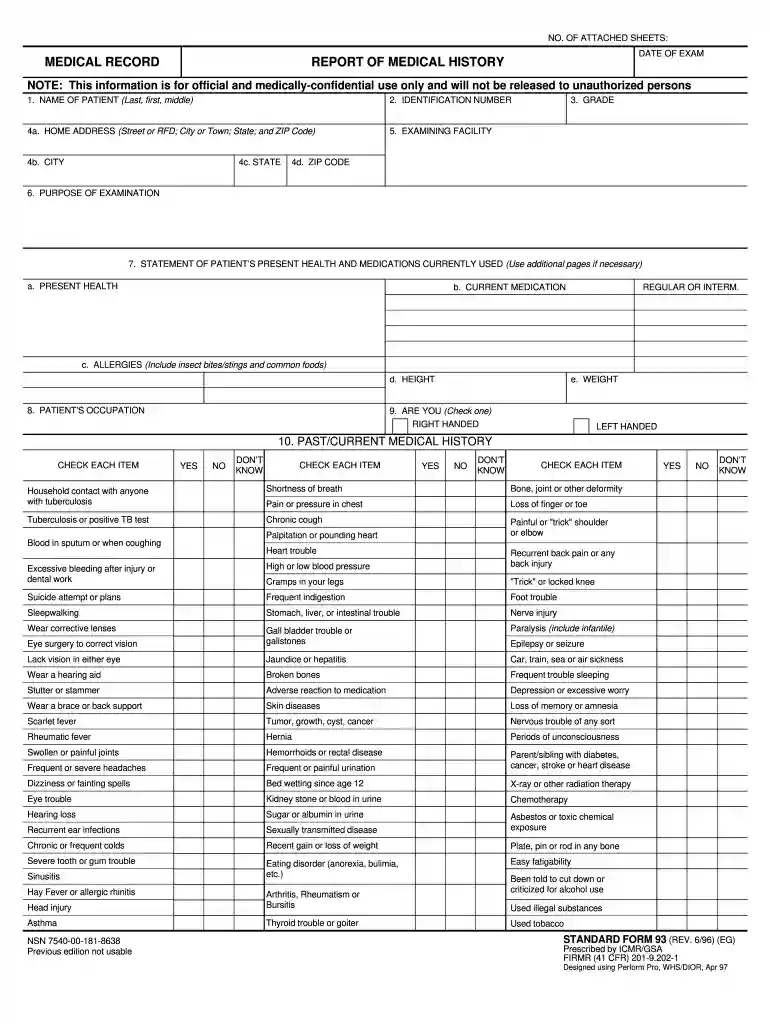
sf 93 Preview on Page 1

Sf 93 2026

Here's how it works

  • 01. Edit your sf 93 online

    Type text, add images, blackout confidential details, add comments, highlights and more.

  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.

  • 03. Share your form with others

    Send sf 93 form via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out sf 93 with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the sf 93 in the editor.
  2. Begin by entering the patient's name in the designated field, ensuring accuracy for identification purposes.
  3. Fill in the identification number and home address, including street, city, state, and ZIP code. This information is crucial for record-keeping.
  4. Specify the examining facility and its location. This helps in tracking where the examination took place.
  5. In section six, clearly state the purpose of the examination. This provides context for medical professionals reviewing the form.
  6. Complete section seven by detailing the patient’s present health status and any medications currently used. Use additional pages if necessary.
  7. Proceed through sections eight to twenty-three, checking each item that applies to ensure comprehensive medical history documentation.
  8. Finally, review all entries for accuracy before signing and dating at the bottom of the form. Ensure that all required fields are completed.

Start using our platform today to fill out your sf 93 easily and for free!

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

Related links

form-sf-93-report-of-medical-history.pdf

STANDARD FORM 93 (REV. 6-96). Prescribed by ICMR/GSA. FIRMR (41 CFR) 201-9.202-1. 4b. CITY. 4c. STATE. 4d. ZIP CODE d. HEIGHT e. WEIGHT. 8. PATIENTS OCCUPATION.Read more

Learn more
MOTOR VEHICLE ACCIDENT REPORT

INSTRUCTIONS: Sections I thru IX are filled out by the vehicle operator. Section X, Items 72 thru 82c are filled out by the operators supervisor.Read more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here