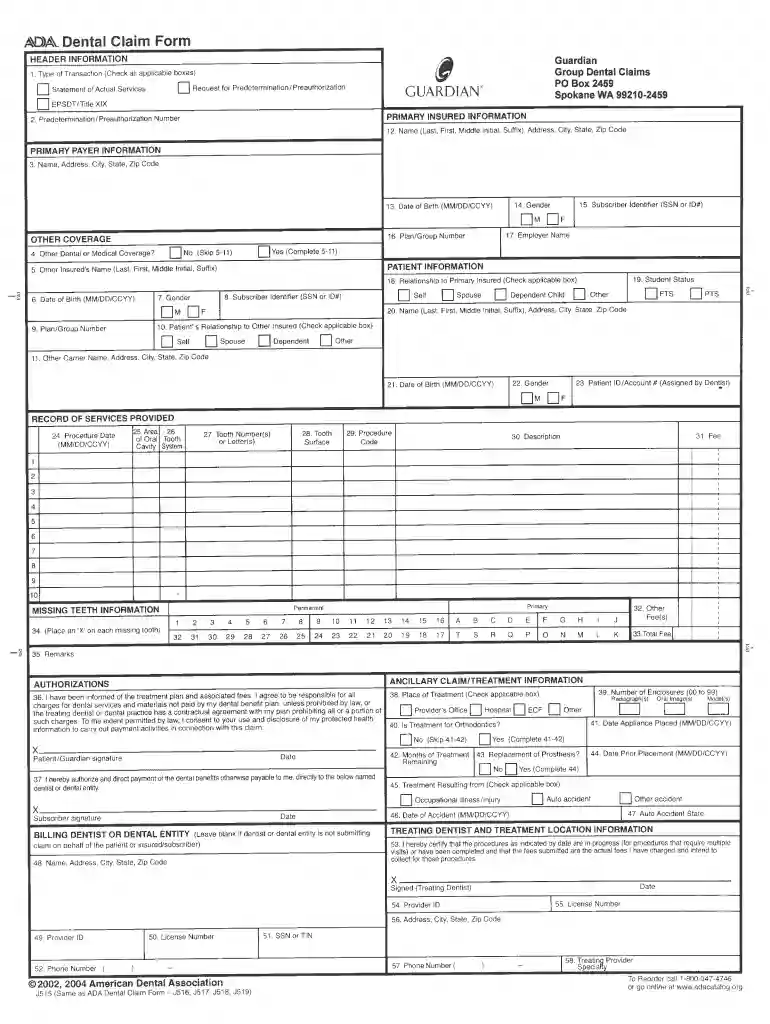
dental claim form 2004 Preview on Page 1

Dental claim form 2004-2026

Here's how it works

  • 01. Edit your form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.

  • 03. Share your form with others

    Send it via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out dental claim form 2004 with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the dental claim form 2004 in the editor.
  2. Begin by filling in Item 3 with the Primary Payer’s name and address. Ensure this information is clear, as it needs to be visible in a standard #10 window envelope.
  3. In the upper-right corner, enter any claim or control number assigned by the payer for easy reference.
  4. Complete all required fields, including full names, addresses, and zip codes. Remember to include four-digit years for all dates.
  5. If you have more procedures than available lines on the form, list additional procedures on a separate claim form.
  6. For coordination of benefits, attach the primary payer's Explanation of Benefits (EOB) if submitting to a secondary payer and indicate amounts paid in Item #35.
  7. Fill out Item 39 regarding enclosures accurately; if none are submitted, enter '00' to confirm no attachments are missing.
  8. Complete Item 43 based on whether you are replacing a prosthesis. Follow the specific instructions provided for each scenario.
  9. Finally, ensure that the treating dentist signs and dates the certification section (Item 53) before submission.

Start using our platform today to fill out your dental claim form 2004 easily and for free!

See more dental claim form 2004 versions

We've got more versions of the dental claim form 2004 form. Select the right dental claim form 2004 version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20064.9 Satisfied (46 Votes)
20044.2 Satisfied (90 Votes)
20024 Satisfied (43 Votes)

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

Related links

Dental Claim Form

I hereby authorize and direct payment of the dental benefits otherwise payable to me, directly to the below named dentist or dental entity. Date. SubscriberRead more

Learn more
Pub 100-04 Medicare Claims Processing

Nov 3, 2014 Effective for claims received on or after April 1, 2004, on the Form CMS-1500, only one name, address and ZIP code may be entered in the block.Read more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here