pediatric dental referral form Preview on Page 1

Pediatric dental referral form 2026

Here's how it works

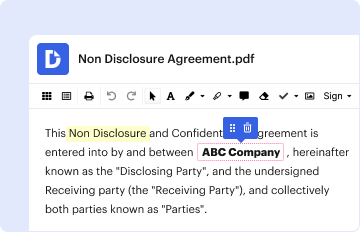
  • 01. Edit your pediatric dental referral form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

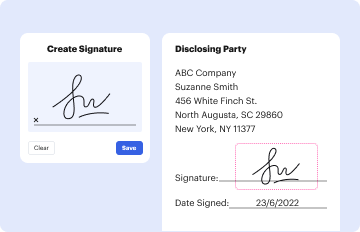
  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
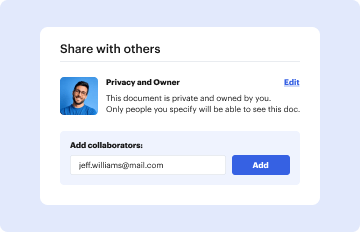
  • 03. Share your form with others

    Send pediatric dental referral form via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out pediatric dental referral form with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the pediatric dental referral form in the editor.
  2. Begin by entering the date at the top of the form. This helps track when the referral was made.
  3. Fill in the patient information section, including last name, first name, middle initial, birth date, and gender. Ensure accuracy for proper identification.
  4. Provide contact numbers: home, work, and cell/message. This ensures that you can be reached easily regarding the referral.
  5. Complete the address fields including street, city, state, and zip code to ensure correct correspondence.
  6. Indicate the reason for referral by checking one of the options provided: treatment, toothache, or consultation.
  7. In the treatment completed section, check any relevant boxes that apply to previous treatments received by the patient.
  8. Fill out insurance information accurately. If applicable, provide details about private insurance or OHP/Washington coverage.
  9. Lastly, include any additional comments or special needs considerations in the comments section before submitting your form.

Start using our platform today to streamline your pediatric dental referrals for free!

See more pediatric dental referral form versions

We've got more versions of the pediatric dental referral form form. Select the right pediatric dental referral form version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20174.9 Satisfied (52 Votes)

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

Related links

REFERRAL FORM

Pediatric Dentistry Clinic. Phone: (312) 996-7532 Fax: Please Fax this Form to : (312) 996-1981 or Email to dentpediatrics@uic.edu. Reason for referral: ☐.

Learn more
Dental Services Referral Form

Please check box below that best represents referral source: WIC private physician general dentist. Early Head Start well-child clinic pediatric dentist.Read more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here