




Here's how it works
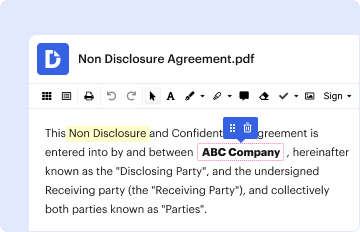
01. Edit your aprn protocol online
Type text, add images, blackout confidential details, add comments, highlights and more.
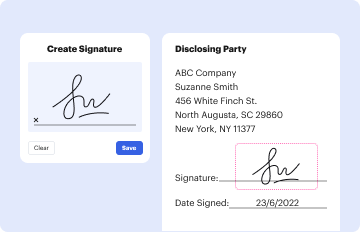
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
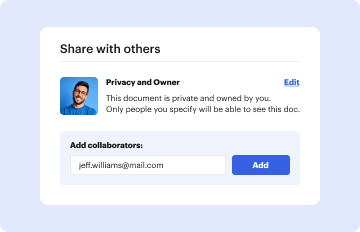
03. Share your form with others
Send nurse protocol agreement georgia via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out aprn protocol agreement with our platform

- Click ‘Get Form’ to open the aprn protocol agreement in the editor.
- Begin by filling in the delegating physician's information. Enter their last name, first name, Georgia license number, and DEA registration number. If applicable, check the boxes indicating if they are a Georgia state, county, or city employee and provide proof of employment.
- Next, specify the degree (MD or DO) and describe the practice area and specialty. Include the number of locations where the APRN will be practicing under this agreement.
- Fill in the primary practice address for the APRN. Ensure all fields such as street number, street name, suite number (if any), city, state, phone number, fax number (optional), zip code, and county are accurately completed.
- Provide details for the Advanced Practice Registered Nurse (APRN), including their DEA registration and RN number. Specify their type (e.g., Nurse Practitioner) and check if pending or will apply later.
- Complete sections regarding license history for both the delegating physician and APRN. Include current license expiration dates and any restrictions on licenses.
- Finally, ensure both parties sign and date the document. Enter required email addresses for communication purposes.
Start using our platform today to streamline your aprn protocol agreement process for free!
Fill out aprn protocol agreement online
It's free
It's free
See more aprn protocol agreement versions
We've got more versions of the aprn protocol agreement form. Select the right aprn protocol agreement version from the list and start editing it straight away!
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


