cms 1490s Preview on Page 1

1490s form 2026

Here's how it works

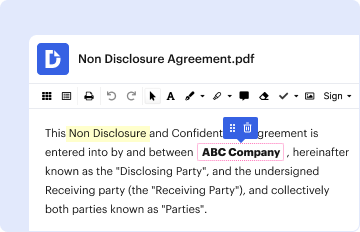
  • 01. Edit your cms 1490s online

    Type text, add images, blackout confidential details, add comments, highlights and more.

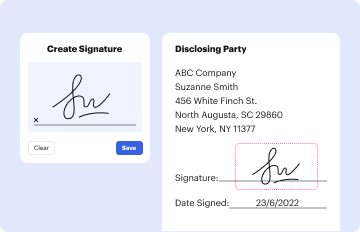
  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
  • 03. Share your form with others

    Send 1490s form via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out 1490s form with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the 1490s form in the editor.
  2. In Block 1, enter your name as it appears on your Medicare Card (Last Name, First Name, Middle Name).
  3. For Block 2, input your Health Insurance Claim Number exactly as shown on your Medicare card and select the appropriate box for the patient’s sex.
  4. In Block 3, provide your mailing address and telephone number. If this is a new address, check the corresponding box.
  5. Describe the illness or injury in Block 4. Indicate if it was related to employment or an accident by checking the appropriate boxes.
  6. Complete Block 5 if you have additional medical coverage. Provide details about other insurance or assistance programs.
  7. Sign and date the form in Block 6. If unable to sign, mark an (X) and have a witness sign as well.

Start using our platform today to fill out your 1490s form easily and for free!

See more cms 1490s versions

We've got more versions of the cms 1490s form. Select the right cms 1490s version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20214.8 Satisfied (62 Votes)
20184.2 Satisfied (53 Votes)
20054 Satisfied (57 Votes)
19874 Satisfied (53 Votes)

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

Related links

42 CFR 424.32 - Basic requirements for all claims.

CMS-1490SRequest for Medicare payment. (For use by a patient to request payment for medical expenses.) The CMS-1490S is also available at local Social

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here