




Here's how it works
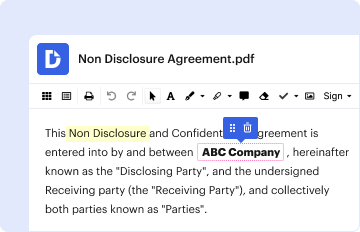
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.
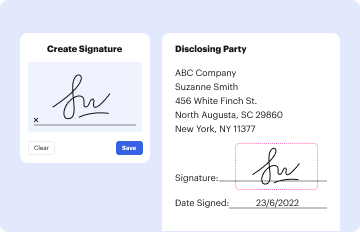
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out REQUEST FOR AND AUTHORIZATION TO RELEASE with our platform

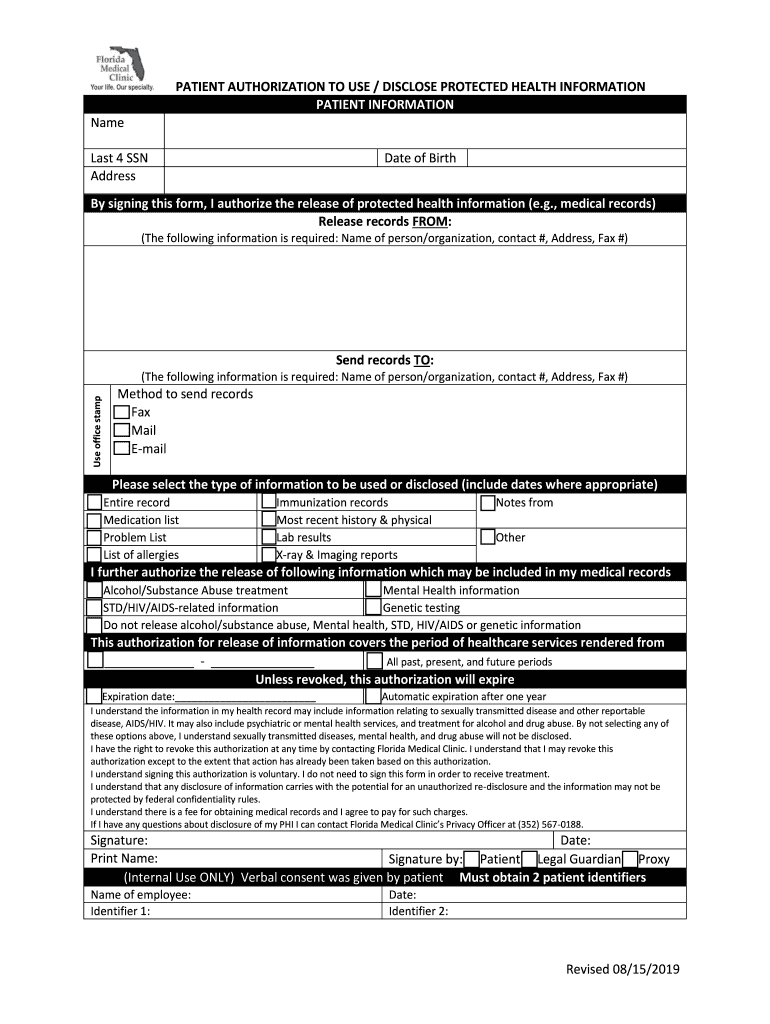
- Click ‘Get Form’ to open the REQUEST FOR AND AUTHORIZATION TO RELEASE in the editor.
- Begin by filling in your personal information in the PATIENT INFORMATION section, including your name, last four digits of your Social Security Number, address, and date of birth.
- In the 'Release records FROM' section, provide the required details of the person or organization releasing your records, including their name, contact number, address, and fax number.
- Next, complete the 'Send records TO' section with similar details for the recipient. Use an office stamp if applicable.
- Select your preferred method for sending records: Fax, Mail, or E-mail.
- Indicate which type of information you wish to disclose by checking the appropriate boxes. Be sure to include any relevant dates where necessary.
- If applicable, authorize the release of sensitive information by checking the corresponding boxes.
- Specify the period for which this authorization is valid by filling in dates or selecting 'All past, present, and future periods.'
- Review all sections carefully before signing and dating at the bottom. Ensure you select who is signing (Patient, Legal Guardian, Proxy).
Start using our platform today to easily fill out and manage your REQUEST FOR AND AUTHORIZATION TO RELEASE form online for free!
Fill out REQUEST FOR AND AUTHORIZATION TO RELEASE online
It's free
It's free
See more REQUEST FOR AND AUTHORIZATION TO RELEASE versions
We've got more versions of the REQUEST FOR AND AUTHORIZATION TO RELEASE form. Select the right REQUEST FOR AND AUTHORIZATION TO RELEASE version from the list and start editing it straight away!
Got questions?
We have answers to the most popular questions from our customers. If you can't find an answer to your question, please contact us.
Contact us
What is a VA 21 4142 authorization for release of information?
Use VA Form 21-4142 to give us permission to obtain your personal information from a non-VA source like a private doctor or hospital. Examples of personal information may include your medical treatment, hospitalizations, psychotherapy, or outpatient care.
What is an authorization and release form?
A medical authorization release form is a form that provides insurance companies with the authority to delve into your medical records.
How do you write an authorization to release information?
Begin by specifying your name, the entity authorized to disclose information, and the individuals or entities you authorize to receive it. Indicate the specific information and purpose for which it will be disclosed, add an expiration date or event, and sign and date the form to confirm your consent.
How to write an authorization to release information?
Clearly state your name and that youre writing to grant authorization to another individual or organization. In the body of your letter, identify the parties involved, specify the authority youre granting, define the duration, and include any other necessary information.
What is a letter of authority to release information?
This Disclosure Authorisation Letter (previously known as an Authorisation to Release Confidential Information) refers to a Confidentiality Agreement and authorises a party to that agreement to release certain information to a named party.
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


People also ask
What are the 8 requirements of a valid authorization to release information?
8 Key Elements of a Compliant Medical Records Release Form Patient Information. Purpose of Request. Dates of Service. Recipient Information. Valid Authorization Signature. Date of Signature. Restrictions or Limitations. Revocation Clause.
How do you write an authorization statement?
5 steps to write a letter of authorization. Identify the parties involved. Specify the authority granted. Define the duration of the agreement. Include any necessary details. Sign the document.