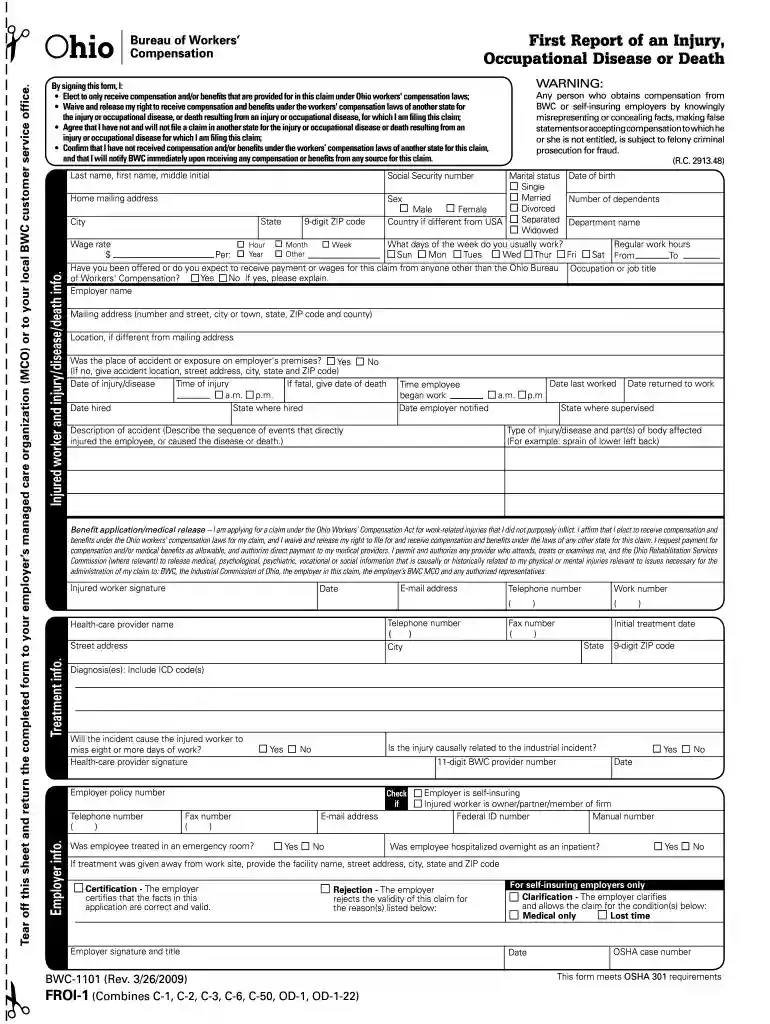
injury collision Preview on Page 1

Accident form 2026

Here's how it works

  • 01. Edit your injury collision online

    Type text, add images, blackout confidential details, add comments, highlights and more.

  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
  • 03. Share your form with others

    Send it via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out accident form with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the accident form in the editor.
  2. Begin by entering your personal information, including your last name, first name, middle initial, and social security number. Ensure accuracy as this information is crucial for processing your claim.
  3. Fill in details about the injury or occupational disease. Specify the date of injury, time of injury, and provide a description of the accident. This section is vital for establishing the context of your claim.
  4. Complete the employment details section by providing your employer's name, address, and job title. Indicate whether the accident occurred on employer premises and include any relevant dates regarding your employment.
  5. Review all sections carefully before signing. Ensure that you have filled out all required fields accurately to avoid delays in processing your claim.

Start filling out your accident form today for free using our platform!

See more injury collision versions

We've got more versions of the injury collision form. Select the right injury collision version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20094.8 Satisfied (40 Votes)

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

Related links

ACCIDENT REPORT LOUISIANA STATE DRIVER SAFETY

Exact Location of Accident (Specify). State Drivers Signature. Name of Drivers immediate Supervisor and Phone No. EMAIL form to : 6410stateofLouisiana@Read more

Learn more
Motor Vehicle Crash Operator Report

Please carefully complete all sections of this form that apply to your crash, circling the answer where appropriate. Illegible reports will be returned to you.Read more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here