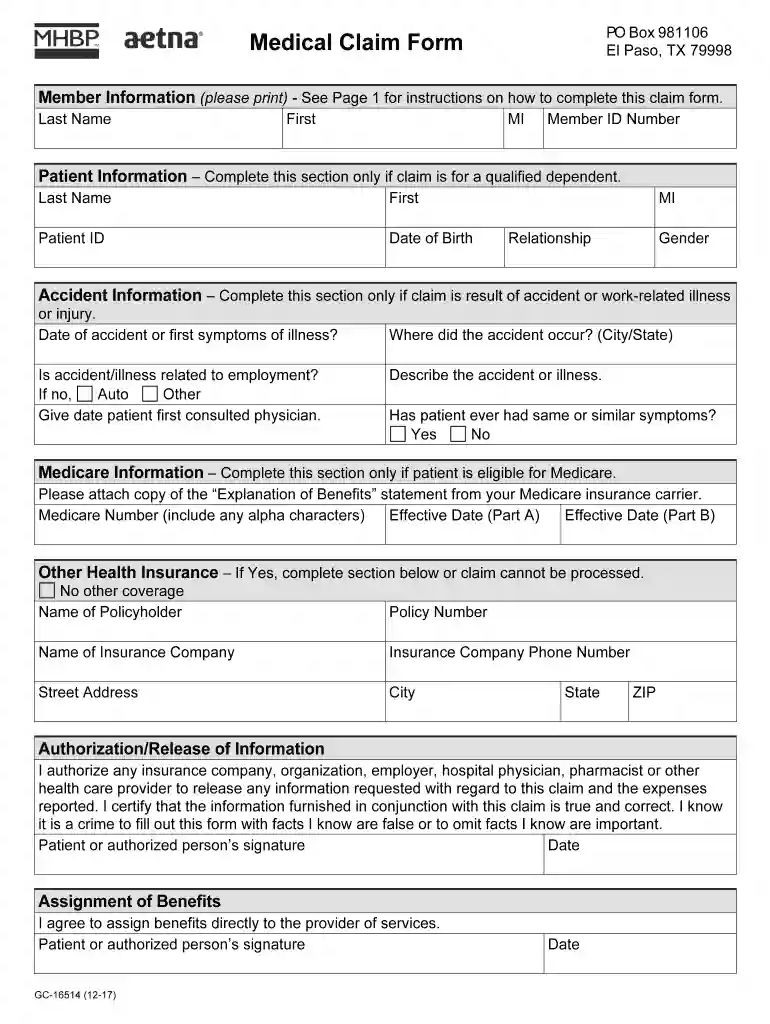
mhbp claim form Preview on Page 1

Mhbp form 2026

Here's how it works

  • 01. Edit your mhbp claim form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.

  • 03. Share your form with others

    Send mhbp form via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out mhbp form with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the mhbp form in the editor.
  2. Begin by filling out the Member Information section. Enter your last name, first name, middle initial, and member ID number accurately.
  3. Next, complete the Patient Information section if the claim is for a qualified dependent. Include their last name, first name, patient ID, date of birth, relationship, and gender.
  4. If applicable, provide details in the Accident Information section. Specify the date of the accident or first symptoms and indicate if it’s work-related.
  5. Fill out Medicare Information only if eligible. Attach a copy of the Explanation of Benefits from your Medicare carrier.
  6. Complete the Other Health Insurance section if you have additional coverage. Provide policyholder details and insurance company information.
  7. Sign in the Authorization/Release of Information section to allow processing of your claim and in the Assignment of Benefits section to authorize direct payment to your provider.
  8. Finally, check with your provider about filing claims on your behalf. If not, attach all necessary documents and mail them to the address provided on the form.

Start using our platform today for free to streamline your mhbp form completion!

See more mhbp claim form versions

We've got more versions of the mhbp claim form form. Select the right mhbp claim form version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20174.8 Satisfied (78 Votes)
20174.3 Satisfied (65 Votes)

be ready to get more

Complete this form in 5 minutes or less

Got questions?

We have answers to the most popular questions from our customers. If you can't find an answer to your question, please contact us.

MHBP is a worldwide health plan backed by the strength of the Aetna network. For over 60 years, MHBP has served all federal and postal service employees, and annuitants, offering comprehensive benefits at affordable rates.
To become a member or associate member: If you are a non-postal employee or an annuitant, you will automatically become an associate member of the National Postal Mail Handlers Union upon enrollment in MHBP.
The MHBP Consumer Option is a high-deductible health plan with a health savings account (HSA).

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

Related links

Mail Handlers Benefit Plan brochure

Take form CA-16 and form OWCP-1500/HCFA-1500 to your provider, or send it to your provider as soon as possible after treatment, to avoid complications about

Learn more
Medical Benefits - Claim Instructions and Form

form. Receipt must contain: - drug name. - nature of illness or injury. - purchase date. - quantity. - prescription number. - charge. - pharmacy name/address.Read more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here