





Here's how it works
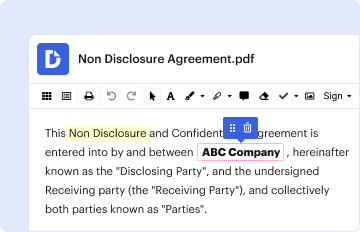
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.
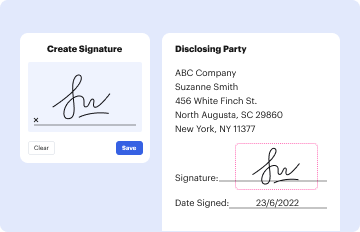
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
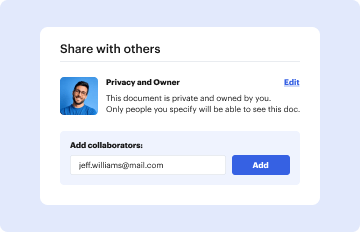
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out Pharmacy Provider Reconsideration with our platform

- Click ‘Get Form’ to open the Pharmacy Provider Reconsideration in the editor.
- Begin by filling out the Patient Information section. Enter the Patient Name, Date of Birth, and Member ID clearly.
- Next, provide details for the Contact Person, including their Office Phone and Office Fax numbers.
- Indicate the Date of Denial and include any Additional Diagnosis Code(s) (ICD-10) relevant to the case.
- In the Reason given for original denial section, check all applicable boxes that explain why the request was denied.
- Finally, ensure that the Prescriber’s Signature is included along with the date. Review all fields for completeness and legibility before submission.
Start using our platform today to streamline your Pharmacy Provider Reconsideration process for free!
Fill out Pharmacy Provider Reconsideration online
It's free
It's free
See more Pharmacy Provider Reconsideration versions
We've got more versions of the Pharmacy Provider Reconsideration form. Select the right Pharmacy Provider Reconsideration version from the list and start editing it straight away!
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


