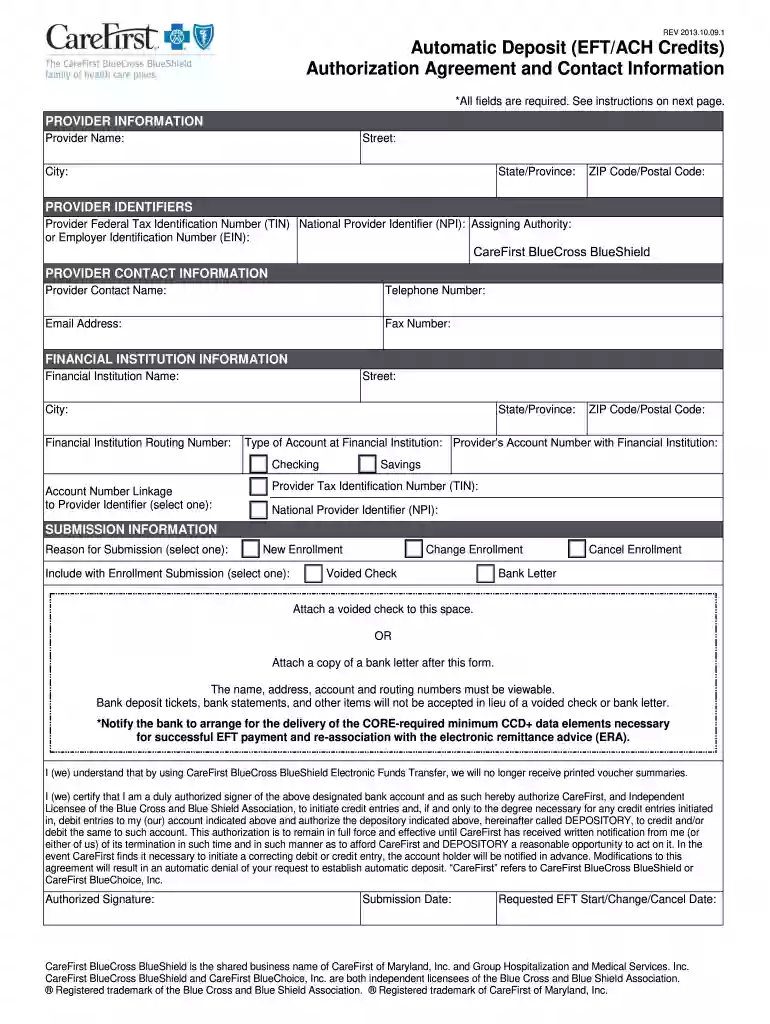
employer code Preview on Page 1

Carefirst eft form 2026

Here's how it works

  • 01. Edit your employer code online

    Type text, add images, blackout confidential details, add comments, highlights and more.

  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.

  • 03. Share your form with others

    Send carefirst eft via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out carefirst eft form with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the carefirst EFT form in the editor.
  2. Begin by filling out the PROVIDER INFORMATION section. Enter your legal provider name, street address, city, state/province, and ZIP code.
  3. Next, complete the PROVIDER IDENTIFIERS section. Input your Federal Tax Identification Number (TIN) or Employer Identification Number (EIN), along with your National Provider Identifier (NPI) and assigning authority.
  4. In the PROVIDER CONTACT INFORMATION section, provide a contact name, telephone number, email address, and fax number for any inquiries related to EFT.
  5. Fill out the FINANCIAL INSTITUTION INFORMATION. Include the financial institution's name, address details, routing number, account type (checking or savings), and your account number.
  6. Select the reason for submission in the SUBMISSION INFORMATION section. Choose from options like New Enrollment or Change Enrollment.
  7. Attach a voided check or bank letter as instructed. Ensure all required fields are completed before submitting.
  8. Finally, review all entries for accuracy and submit via email or fax as specified in the instructions.

Start using our platform today to easily fill out your carefirst EFT form online for free!

See more employer code versions

We've got more versions of the employer code form. Select the right employer code version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20134.8 Satisfied (63 Votes)

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

po box 14113 lexington ky

Provider Manual | Maryland Department of Health

This manual provides information for your CareFirst BlueCross BlueShield and CareFirst BlueChoice, Inc. (CareFirst) patients. Per the terms of the Participation.Read more

Learn more
CHECKLIST

SUBMIT CAREFIRST ENROLLMENT FORM. CAREFIRST HEALTH CARD SUBMIT ELECTRONIC FUNDS TRANSFER (EFT) FORM. SUBMITRead more

Learn more
Change Health Care Commercial Par Payer Listing

Please completed enrollment form located on the Provider Relations Page at . 35161. Indiana ProHealth Network. Par. COMMERCIAL M. Claims.Read more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here