




Here's how it works
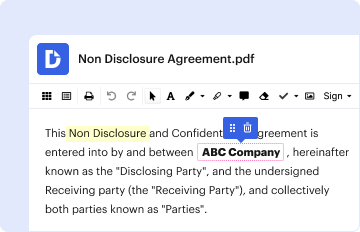
01. Edit your 866 873 8279 online
Type text, add images, blackout confidential details, add comments, highlights and more.
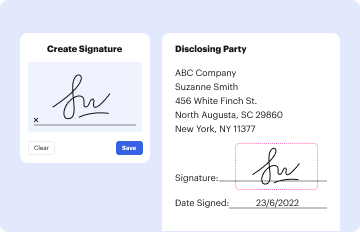
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
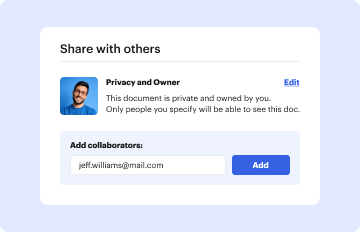
03. Share your form with others
Send cigna pre authorization form via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out 866 873 8279 with our platform

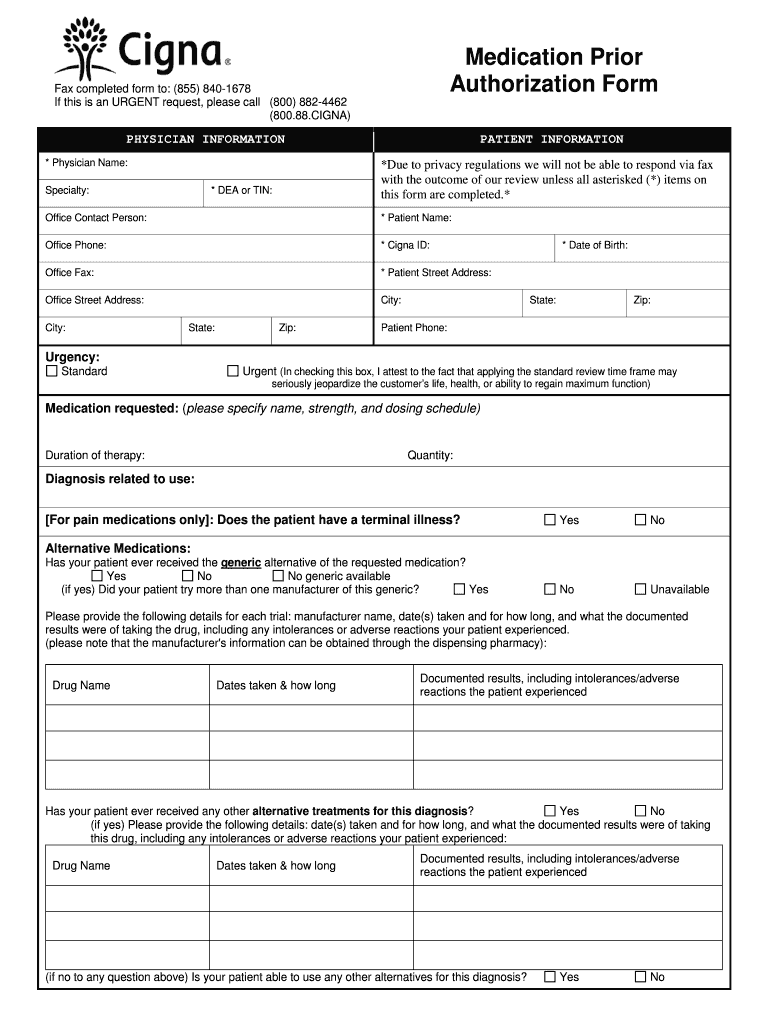
- Click ‘Get Form’ to open the Medication Prior Authorization Form in the editor.
- Begin by filling out the PHYSICIAN INFORMATION section. Enter the Physician Name and Specialty as required.
- Next, complete the PATIENT INFORMATION section. Ensure all asterisked (*) items are filled out, including Patient Name, Cigna ID, Date of Birth, and Patient Street Address.
- Indicate the urgency of the request by selecting either 'Standard' or 'Urgent'. If urgent, confirm that applying standard review time may jeopardize the patient’s health.
- Provide details about the medication requested, including name, strength, dosing schedule, duration of therapy, and quantity.
- Answer questions regarding alternative medications and treatments. Provide detailed information for each trial if applicable.
- Finally, include any additional pertinent information that may support your request before submitting the form.
Start using our platform today to streamline your form completion process for free!
Fill out 866 873 8279 online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


Related forms

Timber Sale Contract Template
The Timber Sale Contract outlines the agreement between a Seller and a Buyer for the sale and purchase of specified timb ...

Wedding Cater Contract Template
The Wedding Catering Contract outlines the terms and conditions for catering services provided by a caterer for a weddin ...

Written Payment Agreement Template
The document is a Written Payment Agreement between a Creditor and a Debtor outlining the terms for repayment of a finan ...

Wedding Photography Contract Template
The Wedding Photography Contract outlines the terms and conditions between a Photographer and Client for wedding photogr ...

Member Managed LLC Operating Agreement Template
The document is a Member Managed Limited Liability Company Operating Agreement that outlines the rights, duties, and res ...

Window Installation Contract Template
The Window Installation Contract outlines the agreement between a Client and Contractor for window installation services ...

Restaurant Consultant Contract Template
The document is a Restaurant Consultant Contract outlining the agreement between a consultant and a restaurant owner for ...

Sale Of Service Contract Template
The Sale of Service Contract outlines the agreement between a service provider and a client, detailing the terms and con ...