




Here's how it works
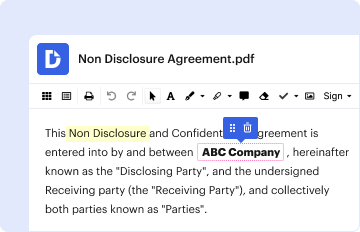
01. Edit your editable nomnc form online
Type text, add images, blackout confidential details, add comments, highlights and more.
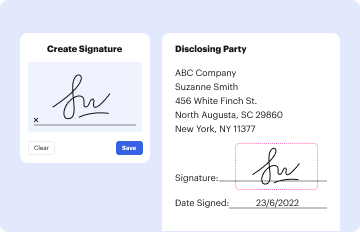
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
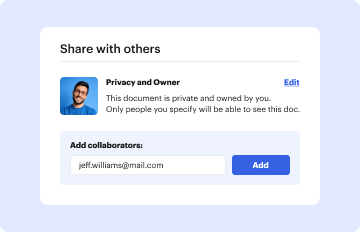
03. Share your form with others
Send nomnc via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out nomnc form with our platform

- Click ‘Get Form’ to open the nomnc form in the editor.
- Begin by entering the 'Patient Name' and 'Patient Number' in the designated fields. Ensure that this information is accurate for proper identification.
- In the section labeled 'The Effective Date Coverage of Your Current Skilled Nursing Facility Services Will End', fill in the date clearly. This is crucial as it indicates when your coverage will cease.
- Review your rights to appeal, which are outlined in the form. Familiarize yourself with these points to understand your options should you wish to contest the decision.
- If you decide to appeal, locate the instructions on how to ask for an immediate appeal. Fill out any necessary details as required by your Quality Improvement Organization (QIO).
- Finally, sign and date the form at the bottom to confirm that you have received this notice and understand your rights regarding coverage termination.
Start using our platform today for free to easily fill out and manage your nomnc form!
Fill out nomnc form online
It's free
It's free
See more nomnc form versions
We've got more versions of the nomnc form form. Select the right nomnc form version from the list and start editing it straight away!
| Versions | Form popularity | Fillable & printable |
|---|---|---|
| 2013 | 4 Satisfied (33 Votes) |
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


