INCIDENT ANALYSIS FORM - Texas Mutual Insurance Company Preview on Page 1

INCIDENT ANALYSIS FORM - Texas Mutual Insurance Company 2026

Here's how it works

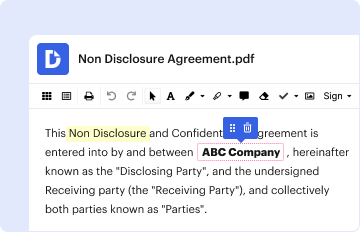
  • 01. Edit your form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

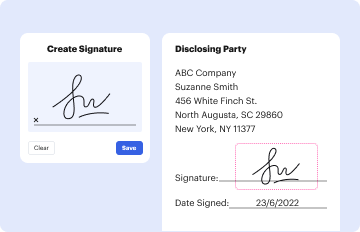
  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
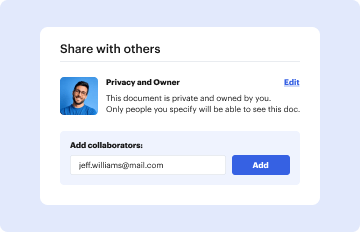
  • 03. Share your form with others

    Send it via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out INCIDENT ANALYSIS FORM - Texas Mutual Insurance Company with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the INCIDENT ANALYSIS FORM in the editor.
  2. Begin by entering today’s date and the date the incident was reported. Fill in your company name, department, supervisor's name, and contact number.
  3. In the 'Name of Person Involved' section, provide the full name of the individual affected by the incident. Continue by filling out their sex, social security number, date of birth, and the date of the incident.
  4. Specify the time and day of the incident along with its exact location. Indicate whether it occurred on employer’s premises and describe the job task being performed at that time.
  5. Complete sections regarding injury details including part of body affected, nature of injury or illness, and any witnesses present during the incident.
  6. Finally, document preventive measures taken to avoid future incidents and provide descriptions from both employee and supervisor perspectives.

Start using our platform today to efficiently complete your INCIDENT ANALYSIS FORM for free!

See more INCIDENT ANALYSIS FORM - Texas Mutual Insurance Company versions

We've got more versions of the INCIDENT ANALYSIS FORM - Texas Mutual Insurance Company form. Select the right INCIDENT ANALYSIS FORM - Texas Mutual Insurance Company version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20064 Satisfied (40 Votes)

be ready to get more

Complete this form in 5 minutes or less

Got questions?

We have answers to the most popular questions from our customers. If you can't find an answer to your question, please contact us.

(800) 859-5995 with questions or concerns. Explore answers about the claim management process in our Employer FAQ.
The Division of Workers Compensation (DWC) Regulates workers compensation benefits in Texas.
As a mutual insurance company, Texas Mutual is solely owned by its policyholders. Good faith stewardship of policyholder assets is, therefore, central to our mission.
Mail: Texas Mutual Insurance Company, P.O. Box 12029, Austin, Texas 78711-2029. Fax: (512) 224-3889.
As the states leading provider of workers compensation, were dedicated to the strength and resiliency of Texas.

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

People also ask

Were thrilled to share that AM Best has upgraded our financial strength rating to A+ (Superior) from A (Excellent).

Related links

Listing of all TDI forms - Texas Department of Insurance

Use this form to report changes to control of a licensed insurance agency; or to report new individuals to be associated with or disassociated from aRead more

Learn more
LawTracker - Law Firm Application Interview Database

Track law firm applications and interview questions to help students succeed.

Learn more
Under the Texas Labor Code, the patient

Apr 23, 2021 Once the employer has completed all information pertaining to the injury the employer should maintain the copy of this report to serve as the.Read more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here