USE THIS FORM TO VERIFY COVERAGE FOR CHIROPRACTIC CARE Preview on Page 1

USE THIS FORM TO VERIFY COVERAGE FOR CHIROPRACTIC CARE 2026

Here's how it works

  • 01. Edit your form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

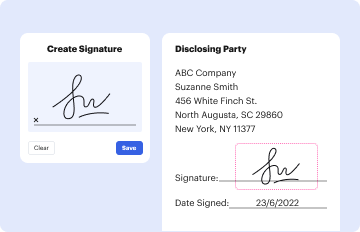
  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
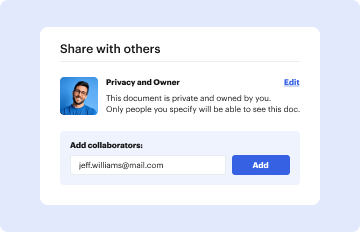
  • 03. Share your form with others

    Send it via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out USE THIS FORM TO VERIFY COVERAGE FOR CHIROPRACTIC CARE with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open it in the editor.
  2. Begin by entering the Patient’s Name and Subscriber’s Name in the designated fields. This information is crucial for identifying the insurance coverage.
  3. Indicate the Relationship to Patient, Insurance Company, and provide the Insurance Phone Number. These details help streamline communication with your insurance provider.
  4. Fill in the Date and Time of your call, along with the Name of the Insurance Representative you spoke with. This documentation can be helpful for future reference.
  5. Proceed to answer the questions regarding your coverage. For each question, select 'Yes' or 'No' as applicable, and fill in any amounts where indicated (e.g., co-pays, deductibles).
  6. Complete any additional questions about therapy coverage and limits. Ensure all fields are filled accurately to avoid delays in processing.
  7. Finally, sign and date the form at the bottom before submitting it back to our office by your second visit.

Start using our platform today for free to simplify your form completion process!

See more USE THIS FORM TO VERIFY COVERAGE FOR CHIROPRACTIC CARE versions

We've got more versions of the USE THIS FORM TO VERIFY COVERAGE FOR CHIROPRACTIC CARE form. Select the right USE THIS FORM TO VERIFY COVERAGE FOR CHIROPRACTIC CARE version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20104.4 Satisfied (36 Votes)

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

Related links

molina-dual-options-star-plus-mmp-provider-manual.

by C Medicaid Cited by 1 Claims are submitted using the CMS Health insurance Claim Form 1500. For EA, field #17 (Name of Referring Provider or Other Source) is not a required field. The.Read more

Learn more
Health Questionnaire

Insurance: The Clinics accept assignment for most insurance coverage and will be happy to pre-verify your insurance coverage. You will need to provide yourRead more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here