




Here's how it works
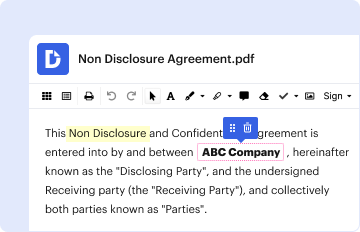
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.
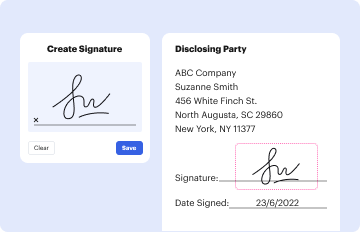
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
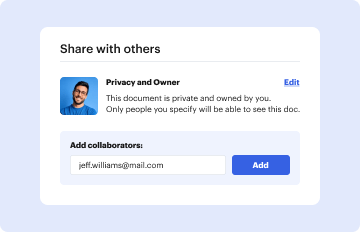
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out personal information preference with our platform

- Click ‘Get Form’ to open it in the editor.
- In Section B, enter your full name, physical street address, city, state, and zip code. If your mailing address differs from your physical address, provide that information as well.
- Move to Section C where you will indicate your preferences regarding sharing personal health information. Select 'Yes' if you want Medicare to share your information or 'No' if you wish to decline sharing.
- Sign and print your full name in the designated areas. If applicable, check the box indicating you are a personal representative and provide the necessary details.
- Finally, refer to Section D for submission instructions. You can either return the form in person or via mail to Indiana University Health ACO, Inc., or call 1-800-MEDICARE for assistance.
Start using our platform today for free and take control of your personal health information preferences!
Fill out personal information preference online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


