cvs prescription mail Preview on Page 1

Cvs caremark fax form 2026

Here's how it works

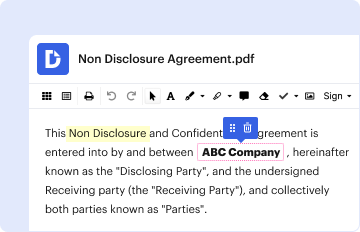
  • 01. Edit your cvs prescription mail online

    Type text, add images, blackout confidential details, add comments, highlights and more.

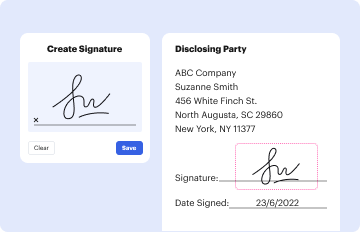
  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
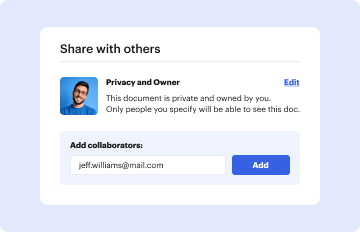
  • 03. Share your form with others

    Send cvs number via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out cvs caremark fax form with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the CVS Caremark Fax Form in the editor.
  2. Begin with Step 1: Patient Information. Fill in the patient's name, date of birth, address, phone number, city, state, ZIP code, and CVS Caremark Member ID. Ensure all details are accurate for seamless processing.
  3. Proceed to Step 2: Prescription Information. Enter the drug name, strength, prescription date, directions for use, quantity needed (90 days or 1 year), and refills for each medication listed. Make sure to double-check this information.
  4. In Step 3: Physician Information Required, provide the prescriber's name, phone number, address, fax number, city, state, ZIP code, NPI number, and DEA number. This section is crucial for verification.
  5. Finally, review all sections for completeness and accuracy before submitting. Once confirmed, fax this form to 1-800-378-0323 or choose to ePrescribe directly through our platform.

Start using our platform today to easily fill out and submit your CVS Caremark Fax Form online for free!

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

18003780323

Formulary Exception/Prior Authorization Request Form

PRESCRIPTION BENEFIT PLAN MAY REQUEST ADDITIONAL INFORMATION OR CLARIFICATION, IF NEEDED, TO EVALUATE REQUESTS . PLEASE FAX COMPLETED FORM TO 1-888-836-0730. IRead more

Learn more
Cvs Pharmacy Prior Authorization Form

Cvs Pharmacy Prior Authorization Form Please respond below and fax this form to cvs Cvs Caremark Formulary Exception Prior Authorization Request Form.Read more

Learn more
CVS/caremark Mail Service Pharmacy Program

Complete the CVS/caremark Mail Service Order Form attached to this letter. Mail the completed form, payment (if required), and your 90-day prescription to

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here