





Here's how it works
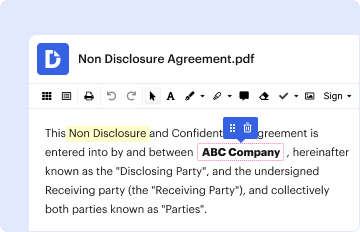
01. Edit your cvs caremark mail order login online
Type text, add images, blackout confidential details, add comments, highlights and more.
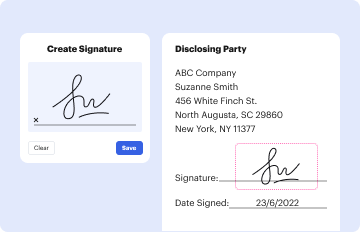
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
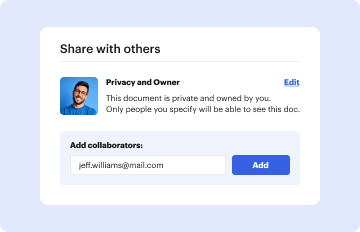
03. Share your form with others
Send caremark mail order login via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out caremark d requestor fill with our platform

- Click ‘Get Form’ to open the caremark d requestor fill in the editor.
- Begin by selecting the appropriate EFT Request Type: New EFT Set-Up, Change to Existing EFT Set-Up, or Cancel EFT. This selection is crucial for processing your request correctly.
- Next, indicate the Pharmacy Type by choosing either Independent or Chain. If you select Chain, ensure to provide your NCPDP# and Chain Code#.
- Fill in the Pharmacy/Chain Name and complete the Address section with street, city, state, and zip code.
- Provide Contact Name, Phone number, Fax number, and both Contact Email Address and Pharmacy/Chain Email Address for communication purposes.
- In the EFT Banking Information section, enter your Bank Account #, ABA Routing Number, Account Name, and select Account Type as Checking. Also include Bank Name and Bank Address/City/St/Zip.
- Remember to submit a copy of a voided check or deposit slip as page 2 of this request. This is a required step for processing your EFT setup.
- Finally, sign and date the form at the bottom before faxing it to Caremark Med D EFT at 480-614-7443. Ensure all information is accurate to avoid delays.
Start using our platform today for free to streamline your document editing and submission process!
Fill out caremark d requestor fill online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


