




Here's how it works
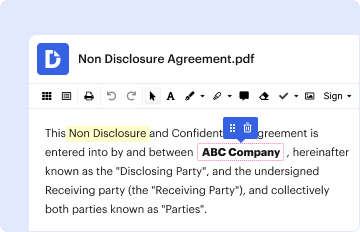
01. Edit your ihss increase hours form online
Type text, add images, blackout confidential details, add comments, highlights and more.
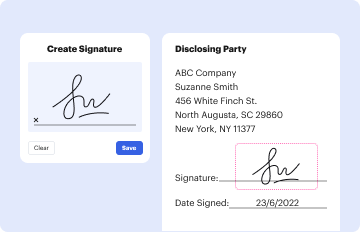
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
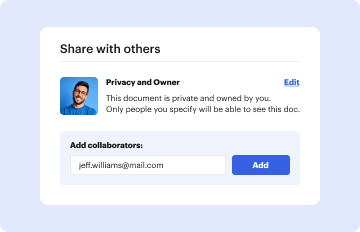
03. Share your form with others
Send ihss request more hours form online via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out IHSS CARE PROVIDER with our platform

- Click ‘Get Form’ to open the IHSS CARE PROVIDER document in the editor.
- Begin by filling out the 'Applicant Submission' section. Enter your last name, first name, and any other names you may have (e.g., aliases). Ensure accuracy as this information is crucial for identification.
- Next, complete the 'Personal Information' section. Provide your date of birth, sex, height, weight, eye color, hair color, and driver's license number. This data helps verify your identity.
- In the 'Home Address' section, input your street address or P.O. Box along with city, state, and ZIP code. This ensures that all correspondence reaches you without delay.
- Fill in the 'Level of Service' and any additional identifiers such as Social Security Number or Miscellaneous Number if applicable. This information is vital for processing your request.
- Finally, review all entries for accuracy before saving or submitting the form through our platform to ensure a smooth processing experience.
Start using our platform today to easily fill out your IHSS CARE PROVIDER form for free!
Fill out IHSS CARE PROVIDER online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


