medical records request form pdf Preview on Page 1

Medical records request form download 2026

Here's how it works

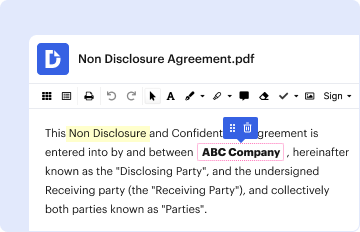
  • 01. Edit your medical records request form pdf online

    Type text, add images, blackout confidential details, add comments, highlights and more.

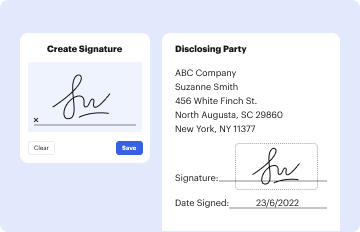
  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
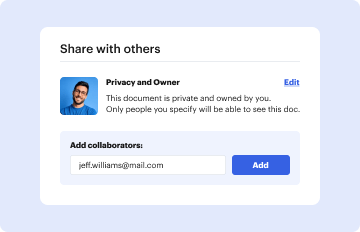
  • 03. Share your form with others

    Send it via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out medical records request form download with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the medical records request form in the editor.
  2. Begin by entering your personal information. Fill in your name, date of birth, and any previous names you may have used.
  3. Provide your contact details, including a telephone number and email address, ensuring that they are accurate for follow-up communication.
  4. In the 'My Authorization' section, check all applicable boxes to specify which health care information you authorize for disclosure.
  5. Indicate the specific treatment or condition related to your health care information if necessary, along with relevant dates.
  6. Designate where this information should be sent by filling in the recipient's name or organization and their contact details.
  7. Review your rights outlined in the form and ensure you understand them before signing at the bottom. Include your printed name and relationship if applicable.

Start using our platform today to easily fill out and manage your medical records request form for free!

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

Related links

patient records - copying request form

Sep 24, 2018 PATIENT RECORDS - COPYING REQUEST FORM. (PATIENT TRANSITIONING TO ANOTHER PROVIDER). Patients Name: (please print). Last. First. Middle. Home

Learn more
VA Form 10-5345

The information requested on this form is solicited under Title 38 U.S.C. The form authorizes release of information in accordance with the Health Insurance.

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here