FMLA FORM-3 B Preview on Page 1

FMLA FORM-3 B 2026

Here's how it works

  • 01. Edit your form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

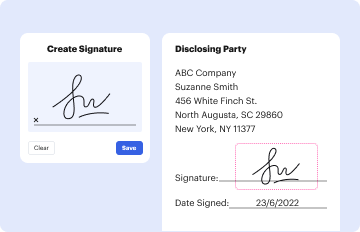
  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
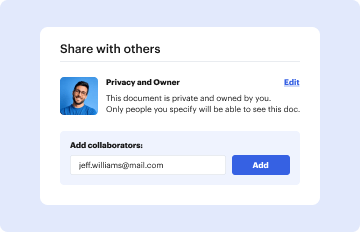
  • 03. Share your form with others

    Send it via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out FMLA FORM-3 B with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open FMLA FORM-3 B in the editor.
  2. Begin with Section 1, where your employer's details are required. Fill in the college name, address, and contact information accurately.
  3. In Section II, provide your name and the name of the family member you will care for. Describe the type of care you will provide and estimate the leave needed.
  4. Proceed to Section III, which is for the health care provider. Ensure they complete all applicable parts regarding medical facts and care needed.
  5. In Part A, the health care provider should specify details about the condition, including dates of treatment and any necessary follow-up visits.
  6. In Part B, detail how much care is needed by answering questions about incapacity periods and any episodic flare-ups that may occur.
  7. Finally, ensure that the health care provider signs and dates the form before submission.

Start using our platform today to fill out your FMLA FORM-3 B easily and for free!

See more FMLA FORM-3 B versions

We've got more versions of the FMLA FORM-3 B form. Select the right FMLA FORM-3 B version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20154.8 Satisfied (136 Votes)

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

Related links

Certification of Health Care Provider for Employees Serious

While use of this form is optional, this form asks the health care provider for the information necessary for a complete and sufficient medical certification,Read more

Learn more
PFL Family Care Leave Forms - PFL-1, PFL-3, PFL-4

The employer completes Part B of the Request for Paid Family Leave (Form PFL-1) and returns it to the employee within three business days.

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here