Authorization for Treatment and Release of Information Preview on Page 1

Authorization for Treatment and Release of Information 2026

Here's how it works

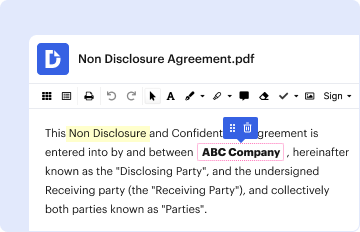
  • 01. Edit your form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

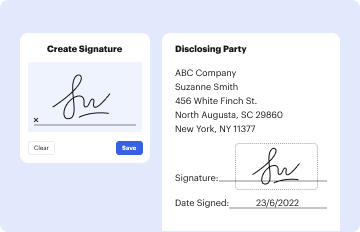
  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
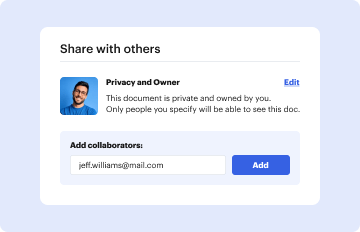
  • 03. Share your form with others

    Send it via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out Authorization for Treatment and Release of Information with DocHub

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the Authorization for Treatment and Release of Information in our editor.
  2. Begin by filling in your name in the designated field. This identifies you as the authorizing party.
  3. Next, provide your signature to validate the authorization. This is crucial for legal purposes.
  4. Enter your contact phone number so that the dental office can reach you if necessary.
  5. Specify your relationship to the child, which helps clarify your authority in this context.
  6. List each child’s name along with their date of birth. This ensures that the authorization applies specifically to them.
  7. Finally, print your name again and confirm your relationship to the child before adding the date of completion.

Start using our platform today to easily complete and manage your Authorization for Treatment and Release of Information!

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

Related links

Authorization to Release or Obtain Health Information

Apr 14, 2003 A separate signed authorization form is required for the use and disclosure of health information for: ✓ Psychotherapy notes ✓ Employment-

Learn more
Forms for Parents - Pittsburgh

To request your childs medical records, complete and sign the Authorization for Release of Protected Health Information (PDF) form. Fax: 412-692-6068 E-mail:

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here