




Here's how it works
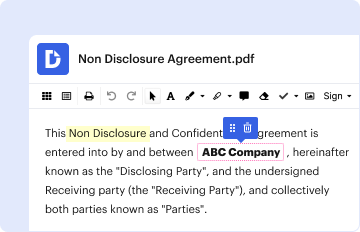
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.
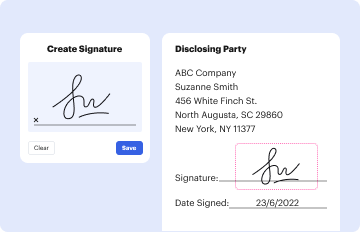
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
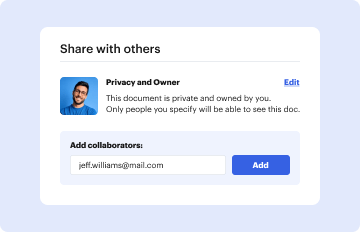
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out EFT CONTACT REQUEST UPDATE Fill Online, Printable, Fillable with our platform

- Click ‘Get Form’ to open the EFT CONTACT REQUEST UPDATE in the editor.
- Begin by completing the Provider Information section. Enter your Provider Name, Doing Business As Name (DBA), and full address including Street, City, State/Province, and Zip Code/Postal Code.
- Next, provide your Provider Identifiers Information. Input your Federal Tax Identification Number (TIN) or Employer Identification Number (EIN).
- If you are adding a new contact, fill in the Delegated (New) Contacts section with the Provider Contact Name, Title, Telephone Number/Ext, Email Address, and Fax Number.
- For replacing an existing contact, ensure that you leave the Delegated Contact section blank if not assigning a delegate.
- Complete the Authorized Signature section by providing the name and title of the person submitting enrollment along with their contact details.
- Finally, sign and date the form before submitting it via email to EFTEnrollment@ChangeHealthcare.com or faxing it to 615-238-9615.
Start using our platform today for free to streamline your document editing and submission process!
Fill out EFT CONTACT REQUEST UPDATE Fill Online, Printable, Fillable online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


