




Here's how it works
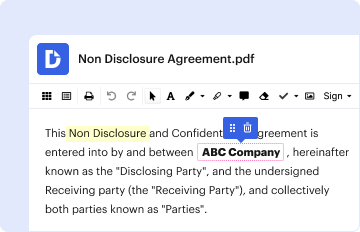
01. Edit your meridian eft enrollment form online
Type text, add images, blackout confidential details, add comments, highlights and more.
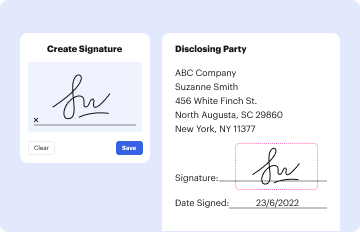
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
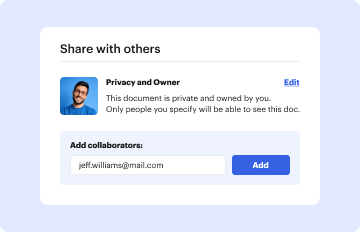
03. Share your form with others
Send meridian eft enrollment via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out Electronic Claims Payment For Providers with our platform

- Click ‘Get Form’ to open the Electronic Claims Payment For Providers in the editor.
- Begin with Part I: Reason for Submission. Select one of the options: New EFT Authorization, Cancel EFT, Revision to Existing Enrollment, or Enroll in Electronic Remittance Advice (ERA).
- In Part II: Pharmacy/Organization Information, fill in your Tax ID, Chain Code/Payment Center ID/NCPDP, Organization Name, Address, City, State, and Zip Code.
- Proceed to Part III: Pharmacy/Organization Contact. Enter the Name, Title, Email Address, Phone Number, and Fax Number of the primary contact.
- In Part IV: Designation of Depository, provide Bank Name, Account Name, Bank Address details including City and State. Fill in Bank Contact Name and Phone Number along with Bank Account Number and Routing Transit Number. Choose between Checking or Savings Account.
- For Part V: Electronic Remittance Advice Information, if applicable, complete the contact information for electronic remittance setup and select your preferred delivery option.
- Finally, sign and date the authorization section at the end of the form. Ensure all required attachments are included before submission.
Start using our platform today to streamline your claims payment process for free!
Fill out Electronic Claims Payment For Providers online
It's free
It's free
See more Electronic Claims Payment For Providers versions
We've got more versions of the Electronic Claims Payment For Providers form. Select the right Electronic Claims Payment For Providers version from the list and start editing it straight away!
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


