how to get ub 04 form from hospital online Preview on Page 1

Fillable ub 04 claim form 2026

Here's how it works

  • 01. Edit your how to get ub 04 form from hospital online online

    Type text, add images, blackout confidential details, add comments, highlights and more.

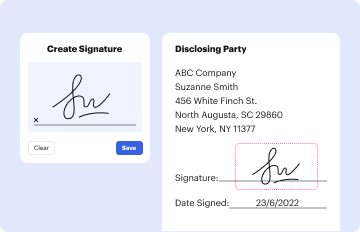
  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
  • 03. Share your form with others

    Send how to get ub 04 form from hospital pdf via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out fillable UB 04 claim form with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the fillable UB 04 claim form in the editor.
  2. Begin by entering the Provider Name and Address in the designated fields at the top of the form. Ensure accuracy as this information is crucial for billing.
  3. Fill in the Patient's Name, Address, Birthdate, and Sex in sections 8 through 12. Double-check these details to avoid any processing delays.
  4. Complete the Type of Bill section (field 4) by selecting the appropriate code that reflects your billing purpose.
  5. In sections 20 through 30, input relevant dates and codes related to occurrences and conditions. This information is vital for claims processing.
  6. Proceed to enter service details including Total Charges and Non-Covered Charges in fields 47 and 48 respectively.
  7. Finally, review all entries for accuracy before saving or exporting your completed form for submission.

Start using our platform today to effortlessly complete your UB 04 claim form online for free!

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

how to get ub 04 form from hospital online free

UB92 Claim Form

UB92 Claim Form. Facility billing name and address. 2. 3 PATIENT CONTROL NO. 4. TYPE. OF. BILL. 5 FED. TAX NO. 6 STATEMENT COVERS PERIOD. 7 COVD. 8 N-C D. 9Read more

Learn more
ub-40-P.pdf

by CDCDC DATE Cited by 1 Submission of this claim constitutes certification that the billing information as shown on the face hereof is true, accurate and complete.Read more

Learn more
Byte Jul 1990 - Absurd

Jul 31, 1990 Form 3579, and fulfillment questions to BYTE Subscriptions. P.O. Box 04 10 France: (I )46092784 The Netherlands : 3 t 02159 46 814.Read more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here