




Here's how it works
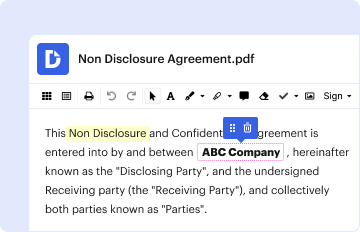
01. Edit your 10 5345a online
Type text, add images, blackout confidential details, add comments, highlights and more.
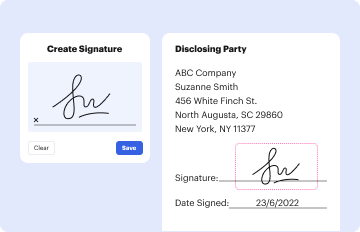
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
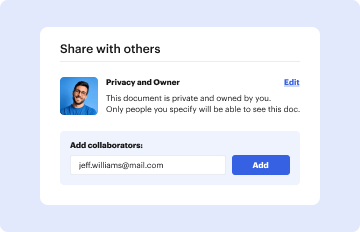
03. Share your form with others
Send 10 5345a form via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out vaform10 5345a with our platform

- Click ‘Get Form’ to open the vaform10 5345a in the editor.
- Begin by entering your last name, first name, and middle initial in the designated fields. This information is crucial for identifying your records.
- Provide your Social Security Number (SSN) and date of birth. Ensure accuracy as this will help locate your health information efficiently.
- In the 'Description of Information Requested' section, check the applicable boxes for the types of records you wish to obtain, such as hospital summaries or outpatient treatment notes. Specify any relevant dates.
- Indicate the facility where you were treated and provide details on how you would like to receive your health information—either in-person or by mail. If by mail, include your complete address.
- Sign and date the form at the bottom. If someone else is signing on your behalf, indicate their authority clearly.
Start using our platform today to fill out your vaform10 5345a easily and for free!
Fill out vaform10 5345a online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


Related forms

Tuberculin Skin Test Consent Form
The document is a consent form for the Tuberculin Skin Test (TST), outlining the individual's eligibility and conditions ...

Certification of Micro Entity Status
The document is a certification form for Micro Entity Status based on gross income, submitted by inventor Roger Paddock ...

IV Medication Orders Form
The document is an IV medication order form for Infusion Associates, detailing the necessary patient information, lab te ...

Form ND-1EXT 2025
The document provides instructions for individuals applying for an extension to file their 2025 North Dakota income tax ...
Form IT-2102 6 Certificate of Income Tax Withheld Tax Year 2025
The document is a Certificate of Income Tax Withheld (IT-2102.6) for New York State, used by employees who have not rece ...
Real Estate Excise Tax Affidavit
The document is a Real Estate Excise Tax Affidavit (Form 84 0001a) required for sales involving multiple location codes ...

Florida Motor Vehicle Dealer License Renewal Application
The document is a renewal application form for motor vehicle, mobile home, or recreational vehicle dealers in Florida. I ...

Dungeons and Dragons Character Record Sheet
The document is a character record sheet for a tabletop role-playing game, specifically designed for Dungeons & Dragons. ...


