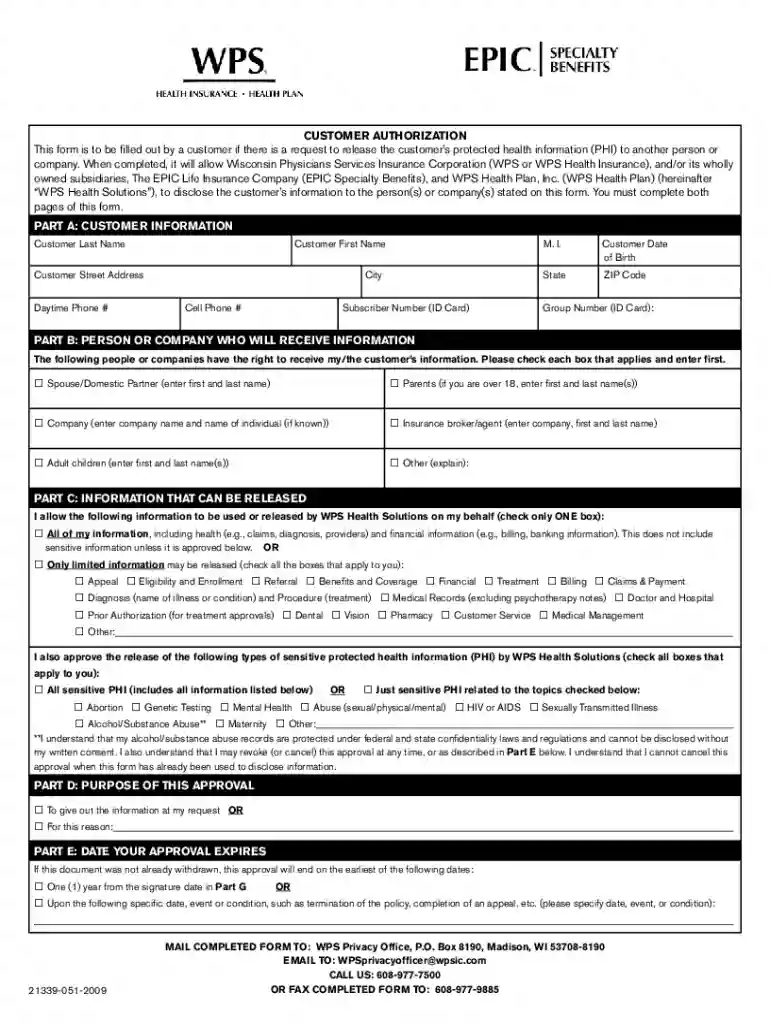
This form is to be filled out by a customer if there is a request to release the customers protected health information (PHI) to another person or Preview on Page 1

This form is to be filled out by a customer if there is a request to release the customers protected health information (PHI) to another person or 2026

Here's how it works

  • 01. Edit your form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.

  • 03. Share your form with others

    Send it via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out the Customer Authorization form for PHI release

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open it in the editor.
  2. Begin with Part A: Enter your personal information, including your last name, first name, address, phone numbers, date of birth, and subscriber number. Ensure all details are accurate.
  3. Move to Part B: Indicate who will receive your information by checking the appropriate boxes and providing names where required.
  4. In Part C: Specify what information can be released by selecting either 'All of my information' or 'Only limited information' and check the relevant boxes.
  5. Complete Part D: State the purpose for this approval by selecting an option that best describes your reason.
  6. Fill out Part E: Indicate when your approval expires by choosing a duration or specifying a date/event.
  7. In Part F: Choose how you would like to receive the information (paper copies, fax, digital copies, or email) and provide necessary details.
  8. Finally, review and sign in Part G. Ensure you understand the implications of releasing your PHI before submitting the form.

Start using our platform today to easily fill out and manage your forms for free!

See more This form is to be filled out by a customer if there is a request to release the customers protected health information (PHI) to another person or versions

We've got more versions of the This form is to be filled out by a customer if there is a request to release the customers protected health information (PHI) to another person or form. Select the right This form is to be filled out by a customer if there is a request to release the customers protected health information (PHI) to another person or version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20204.8 Satisfied (48 Votes)
20164.4 Satisfied (205 Votes)

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

Related links

authorization-for-release-of-protected-health-information-

I, or my authorized representative, hereby authorize NYU Langone Medical Center to share my PHI. I understand that: 1. Information relating to ALCOHOL/DRUGRead more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here