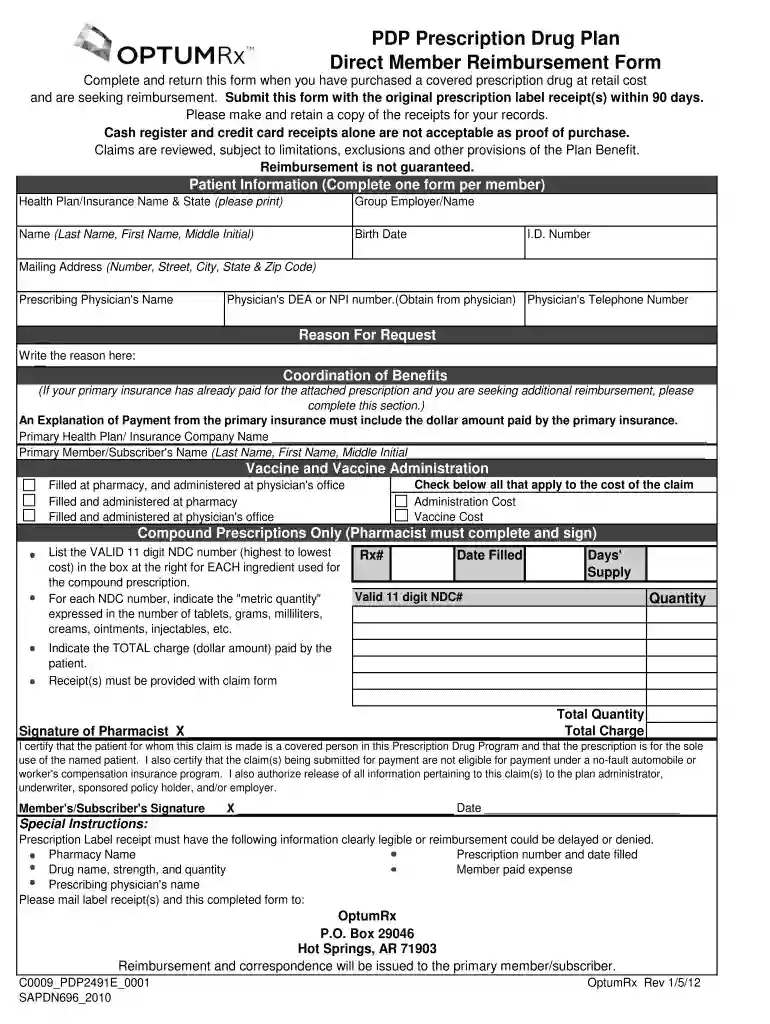
wellcare flex card reimbursement form Preview on Page 1

Direct member reimbursement form 2026

Here's how it works

  • 01. Edit your wellcare flex card reimbursement form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.

  • 03. Share your form with others

    Send wellcare flex card via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out direct member reimbursement form with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the direct member reimbursement form in the editor.
  2. Begin by filling out the Patient Information section. Enter your Health Plan/Insurance Name, Group Employer/Name, and your personal details including your name, birth date, and I.D. number.
  3. Provide your mailing address, prescribing physician's name, and their DEA or NPI number along with their telephone number.
  4. In the Reason For Request section, clearly state why you are seeking reimbursement.
  5. If applicable, complete the Coordination of Benefits section by providing details from your primary insurance regarding any payments made for the prescription.
  6. For vaccine claims, check all relevant boxes indicating where the vaccine was filled and administered.
  7. If submitting a compound prescription, list each ingredient's valid 11-digit NDC number along with its quantity and total charge paid.
  8. Finally, sign and date the form at the bottom to certify that all information is accurate before submitting it along with your receipts.

Start using our platform today to easily fill out your direct member reimbursement form for free!

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

direct member reimbursement form

MAPD PRESCRIPTION REIMBURSEMENT REQUEST

MAPD PRESCRIPTION REIMBURSEMENT REQUEST FORM. Use this form to request reimbursement for covered medications purchased at retail cost. Complete one form perRead more

Learn more
Direct Member Reimbursement Form

You must fill out this entire form in order for us to process your claim(s). 2. Attach all prescription receipt(s) to the back of this form.Read more

Learn more
FFS NMT Member Reimbursement Form MILEAGE LODGING

Enclosed are instructions to help you file a request for reimbursement with Medi-Cal for mileage, lodging and/or meals to and from a covered Medi-CalRead more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here