




Here's how it works
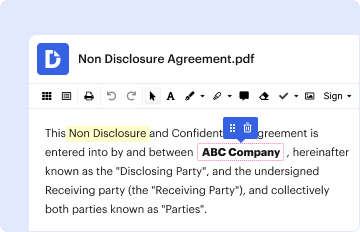
01. Edit your maryland referral form online
Type text, add images, blackout confidential details, add comments, highlights and more.
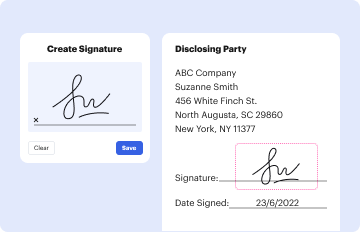
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
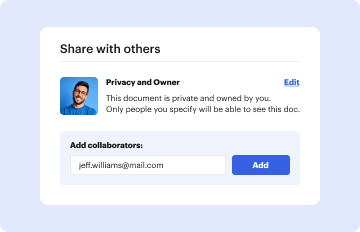
03. Share your form with others
Send maryland uniform consultation referral form via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out primary care physician referral form with our platform

- Click ‘Get Form’ to open the primary care physician referral form in the editor.
- Begin with Section 1: Patient Information. Fill in the patient's name, date of birth, phone number, and ID number. Ensure all fields are completed except for the phone and site number.
- Move to Section 2: Carrier Information. Circle the appropriate carrier name from CareFirst options provided.
- In Section 3: Primary or Requesting Provider, enter your name, specialty, institution/group name, and provider ID. Include your contact information as well.
- Proceed to Section 4: Consultant/Facility Provider. Input the consultant's details including their name, specialty, institution/group name, and provider ID.
- For Section 5: Referral Information, specify the reason for referral along with a brief history or diagnosis.
- In Section 6: Service Desired, indicate the number of visits required; if left blank, it defaults to three visits.
- Finally, complete Section 7: Place of Service by checking 'Office' and filling in the validity date for the referral along with your signature if required.
Start using our platform today to streamline your document editing and ensure a hassle-free experience!
Fill out primary care physician referral form online
It's free
It's free
See more primary care physician referral form versions
We've got more versions of the primary care physician referral form form. Select the right primary care physician referral form version from the list and start editing it straight away!
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


