





Here's how it works
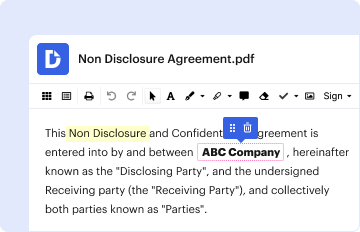
01. Edit your letter of medical necessity fsa gym online
Type text, add images, blackout confidential details, add comments, highlights and more.
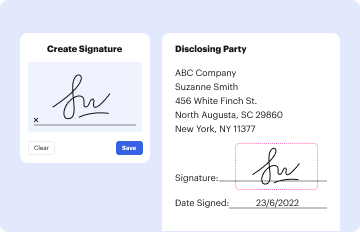
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
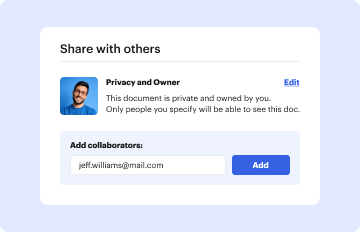
03. Share your form with others
Send letter of medical necessity fsa via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out Letter of Medical Necessity Health Care Flexible

- Click ‘Get Form’ to open it in the editor.
- Begin by entering the 'Date' at the top of the form. This is essential for record-keeping and processing.
- Fill in the 'Employer Name' and 'Employee Name' fields to identify who is requesting the medical necessity.
- Provide the 'SSN/FSA ID' for verification purposes, ensuring confidentiality and accuracy.
- Enter the 'Patient Name' and their 'Relationship to Employee', which helps clarify who is receiving treatment.
- Complete the height, weight, and BMI sections. Use a BMI calculator if needed to determine the patient's BMI accurately.
- In the 'Diagnosis' section, specify any relevant medical conditions related to weight that justify treatment.
- Detail the recommended treatment plan, emphasizing behavioral changes like diet and exercise.
- Indicate how long treatment will be required in the designated field for clarity on expected duration.
- Finally, have your service provider complete their information, including signature and license details, ensuring all necessary authorizations are included.
Start using our platform today to easily fill out your Letter of Medical Necessity for free!
Fill out Letter of Medical Necessity Health Care Flexible online
It's free
It's free
See more Letter of Medical Necessity Health Care Flexible versions
We've got more versions of the Letter of Medical Necessity Health Care Flexible form. Select the right Letter of Medical Necessity Health Care Flexible version from the list and start editing it straight away!
| Versions | Form popularity | Fillable & printable |
|---|---|---|
| 2015 | 4.3 Satisfied (53 Votes) |
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


