




Here's how it works
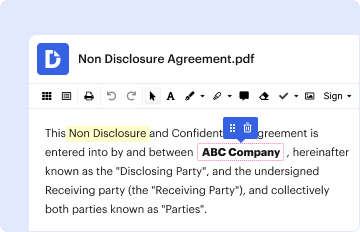
01. Edit your united care form online
Type text, add images, blackout confidential details, add comments, highlights and more.
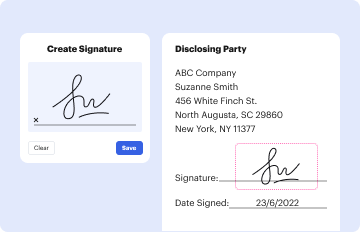
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
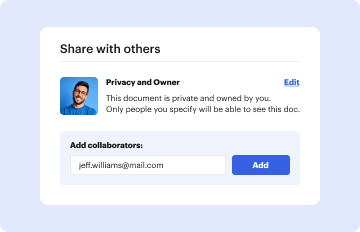
03. Share your form with others
Send united care request via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out the United Care Form with our platform

- Click ‘Get Form’ to open the United Care form in the editor.
- Begin by entering the member information. Fill in the Member ID, date of form completion, control/claim number, date of service, billed amount, and the member's last name, first name, and middle initial.
- Next, provide details about the physician or healthcare professional. Enter the Tax Identification Number (TIN), phone number, email address, and full name as listed on the Provider Remittance Advice (PRA) or Explanation of Benefits (EOB).
- Indicate the reason for your request by selecting from the provided options. If applicable, include any additional comments or expectations regarding this claim reconsideration request.
- Attach any required documents such as a copy of PRA or EOB and other necessary attachments as specified in the form.
Start using our platform today to streamline your document editing and submission process for free!
Fill out united care form online
It's free
It's free
See more united care form versions
We've got more versions of the united care form form. Select the right united care form version from the list and start editing it straight away!
| Versions | Form popularity | Fillable & printable |
|---|---|---|
| 2014 | 4.8 Satisfied (159 Votes) |
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


Related forms

Zav letter sample
The document is a Certificate of Enrolment (Immatrikulationsbescheinigung) issued by a university or college in Germany. ...

Grand Forks-East Grand Forks Transit Development Plan Update
The document is a Request for Proposals (RFP) issued by the Grand Forks – East Grand Forks Metropolitan Planning Organiz ...

Top 10 Best Auburndale FL Handyman ServicesAngie's List
The document is a 'Declaration of Contamination' required by ARMANO Messtechnik GmbH for the repair, maintenance, or dis ...

Blue grant
The document outlines the application process for the Mission Blue Post Assistance Program grant by The American Legion, ...

La communication a sa grande cole - Sup de Pub
The document is an application form for undergraduate admission to CEFAM (Centre d’études Franco-Américain de Management ...

Ir6104
The document is an application form for obtaining a Taxpayer Identification Number (TIN) and/or Access Code for eTAX use ...

Revenue alabama entity-registrationRegister an Entity - Alabama Department of Revenue
The document is a THEMIS Registration Form used to register or update user access for an entity within the THEMIS system ...

Cds attendant
The document outlines the procedures and requirements for hiring and managing attendants in the Consumer Directed Servic ...