




Here's how it works
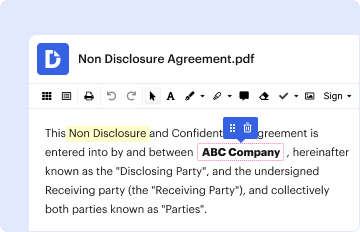
01. Edit your simple sleep online
Type text, add images, blackout confidential details, add comments, highlights and more.
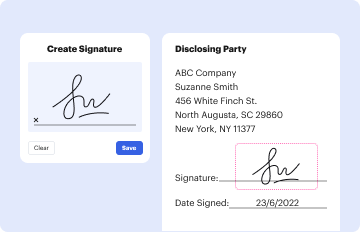
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
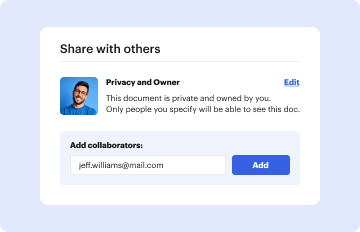
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out Oral Appliance Referral Form - Simple Sleep Services with our platform

- Click ‘Get Form’ to open the Oral Appliance Referral Form in the editor.
- Begin by entering the patient's name in the designated fields for Last Name, First Name, and Middle Initial.
- Fill in the Date of Birth and Patient Phone number to ensure accurate contact information.
- Provide Insurance Information by entering the Insurance Company name, Subscriber Name (Last Name, First Name, Middle Initial), Subscriber DOB, ID Number, and Group Number. Indicate the relationship to the subscriber by selecting Self, Spouse, or Dependent.
- Select the appropriate diagnosis from the list provided. If 'Other' is chosen, specify the condition and its ICD code.
- If applicable, check the box indicating that a sleep study is attached for reference.
- Complete the Statement of Medical Necessity section by providing your Practice Name, Physician’s Name, Practice Address, and signing with your date.
- Once completed, save your document and fax it to (888) 491-6582 or scan and email it to info@simplesleepservices.com.
Start using our platform today for free to streamline your form completion process!
Fill out Oral Appliance Referral Form - Simple Sleep Services online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


