medical release form michigan Preview on Page 1

CHJ-121 Medical Release Form 2026

Here's how it works

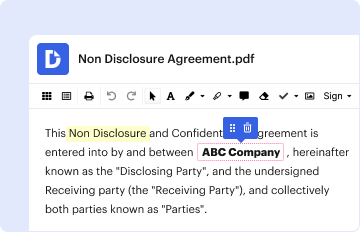
  • 01. Edit your medical release form michigan online

    Type text, add images, blackout confidential details, add comments, highlights and more.

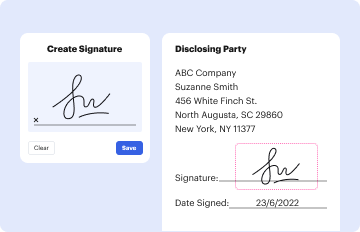
  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
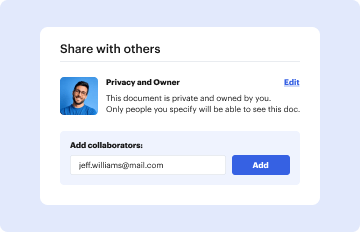
  • 03. Share your form with others

    Send hipaa release form michigan via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out CHJ-121 Medical Release Form with DocHub

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the CHJ-121 Medical Release Form in our platform's editor.
  2. Begin by entering the patient's full name, number, and date of birth in the designated fields. Ensure accuracy as this information is crucial for identification.
  3. Fill in the facility's name and address from which the health information will be released. This helps clarify where the records are coming from.
  4. Next, specify the recipient's address, which in this case is Legal Copy Services, INC. This section ensures that the information reaches the correct party.
  5. Indicate specific dates for the information to be released by filling in both beginning and ending dates. This defines the time frame of records requested.
  6. Select the type of information you wish to release by checking appropriate boxes such as Medical, Dental, or Mental Health. You can also specify other types if necessary.
  7. State the purpose of release; for example, 'Civil Litigation'. This provides context for why this information is being shared.
  8. Finally, sign and date the form at the bottom to authorize disclosure. If applicable, a witness signature may also be required.

Start using our platform today to fill out your CHJ-121 Medical Release Form easily and for free!

be ready to get more

Complete this form in 5 minutes or less

Got questions?

We have answers to the most popular questions from our customers. If you can't find an answer to your question, please contact us.

I was treated in your office [at your facility] between [fill in dates]. I request copies of the following [or all] health records related to my treatment. [Identify records requested (e.g., medical-history form you filled out; physician and nurses notes; test results; consultations with specialists; referrals).]
How to Submit Requests and Receive Copies. To request a copy of your medical records (for personal use or for another healthcare provider), download, print and complete the Release of Information Authorization form. Once completed you may FAX or mail your request to the appropriate medical center listed below.
A medical release form (also known as a medical records release form or authority to release medical information) is a legal document patients can sign to permit healthcare providers to share their private health information with specified third parties.
How you make your request will depend on your providers processes. You may be able to request your record through your providers patient portal. You may have to fill out a form called a health or medical record release form, or request for accesssend an email, or mail or fax a letter to your provider.
I request copies of all health records related to my treatment. I understand you may charge a reasonable fee for copying these records, but will not charge for the time spent locating the records. Please mail the requested records to me at the above address.

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

People also ask

All mail is electronically scanned by JPay for security issues and then sent to the Michigan Department of Corrections where it is reviewed again prior to being released to the prisoner.
The authorization for medical information should be in writing and specify the information being requested and include who is making the request, where the information should be sent and the method. The form should be dates and signed by the patient or their legal representative.

Related links

Concerning Penalties for False Medicaid Claims.

For more information, please contact rebecca.ciota@colorado.edu. Page 2. Ch. 121. Health Care Policy and Financing. 323. CHAPTER 121. HEALTH CARE POLICY AND

Learn more
united states of america

Mar 21, 2019 UNITED STATES OF AMERICA. DEPARTMENT OF HEALTH AND HUMAN SERVICES. FOOD AND DRUG ADMINISTRATION. + + +. CENTER FOR DEVICES AND RADIOLOGICALRead more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here