




Here's how it works
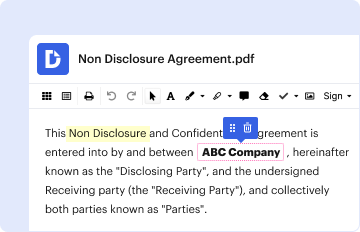
01. Edit your authorization for disclosure of protected health information template online
Type text, add images, blackout confidential details, add comments, highlights and more.
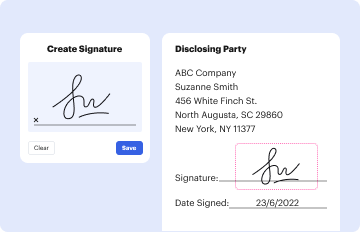
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
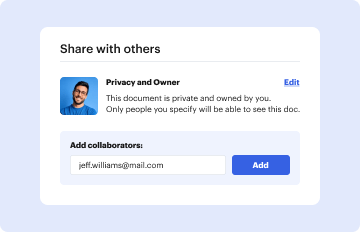
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out Authorization for Use/Disclosure of Protected Health Information

- Click ‘Get Form’ to open it in the editor.
- Begin by entering the Patient Name and Date of Birth in the designated fields. This information is crucial for identifying the individual whose health information is being authorized for release.
- Fill in the Phone Number and Address of the patient. Ensure accuracy as this may be used for follow-up communications.
- Specify the Person(s) or Organization(s) authorized to receive the information. Clearly write their names and addresses to avoid any confusion.
- Indicate your preferred method of contact by filling in the Email, Phone Number, and Fax Number fields.
- Select what specific health information you are authorizing for disclosure. You can choose between Complete Medical Record, Partial Medical Record, or Other Specific Information. Be sure to specify dates where applicable.
- Initial next to any types of information you do not authorize for release, such as Substance Abuse, Mental Health Info, or HIV Info.
- Provide a description of how the information will be used and note that this authorization will expire one year from the date signed unless specified otherwise.
- Sign and date the form at the bottom. If you are signing on behalf of someone else, include your relationship to the patient.
Start using our platform today to easily complete your Authorization for Use/Disclosure of Protected Health Information online for free!
Fill out Authorization for Use/Disclosure of Protected Health Information online
It's free
It's free
Got questions?
We have answers to the most popular questions from our customers. If you can't find an answer to your question, please contact us.
Contact us
What is unauthorized access use and disclosure of protected health information?
A HIPAA authorization form gives covered entities permission to use protected health information for purposes other than treatment, payment, or health care operations. Continue reading to find out when authorization to disclose health information is needed.
What does authorization to disclose protected health information mean?
A HIPAA authorization is a detailed document in which specific uses and disclosures of protected health are explained in full. By signing the authorization, an individual is giving consent to have their health information used or disclosed for the reasons stated on the authorization.
How to fill out authorization to use and disclose health information?
Begin by specifying your name, the entity authorized to disclose information, and the individuals or entities you authorize to receive it. Indicate the specific information and purpose for which it will be disclosed, add an expiration date or event, and sign and date the form to confirm your consent.
What is the authorization to use and disclose protected health information?
Should you sign a HIPAA authorization form? In most cases, the answer is yes. HIPAA is designed to protect patients sensitive health information. Following all HIPAA rules can help to protect healthcare professionals from legal trouble and allow them to better serve their patients.
What is an authorization for disclosure of protected information?
Under the Privacy Rule, a covered entity may use or disclose protected health information pursuant to a copy of a valid and signed Authorization, including a copy that is received by facsimile or electronically transmitted.
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


People also ask
Should I say yes to HIPAA authorization?
A bdocHub is defined as the acquisition, access, use, or disclosure of unsecured PHI that is not permitted by the HIPAA Privacy Rules and compromises the security or privacy of the PHI.