




Here's how it works
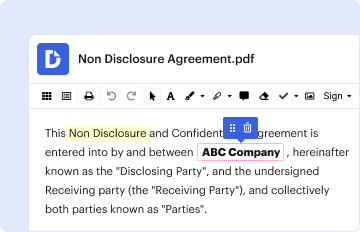
01. Edit your map 14 online
Type text, add images, blackout confidential details, add comments, highlights and more.
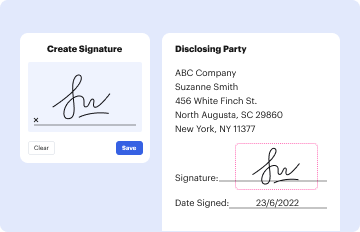
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
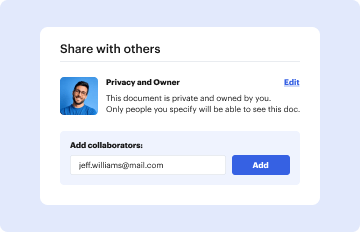
03. Share your form with others
Send map 14 kentucky via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out MAP 14 414 Commonwealth of Kentucky Cabinet for Health and - chfs ky with DocHub

- Click ‘Get Form’ to open it in the editor.
- Begin by filling in your name in the designated field where it states 'I __________ have asked'. This identifies you as the applicant.
- Next, enter the name of your authorized representative in the field labeled 'to apply for Medicaid for me'. This person will act on your behalf.
- In the section that asks why you cannot come to the DCBS office, provide a brief explanation. This is important for understanding your situation.
- Sign the form where indicated, ensuring that both you and your authorized representative complete their respective signature fields.
- Fill out all address and contact information accurately to ensure proper communication regarding your application.
- If applicable, have a witness sign where indicated if you are unable to sign yourself.
Start using our platform today to easily fill out and submit your MAP 14 414 form for free!
Fill out MAP 14 414 Commonwealth of Kentucky Cabinet for Health and - chfs ky online
It's free
It's free
See more MAP 14 414 Commonwealth of Kentucky Cabinet for Health and - chfs ky versions
We've got more versions of the MAP 14 414 Commonwealth of Kentucky Cabinet for Health and - chfs ky form. Select the right MAP 14 414 Commonwealth of Kentucky Cabinet for Health and - chfs ky version from the list and start editing it straight away!
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


