




Here's how it works
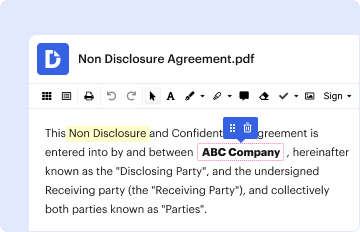
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.
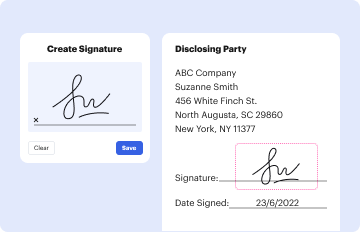
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
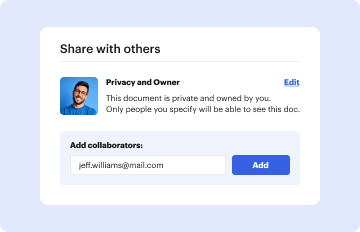
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out authorization to release medical records form with our platform

- Click ‘Get Form’ to open the authorization to release medical records form in the editor.
- Begin by entering your personal information. Fill in your name, date of birth (DOB), and social security number (SSN) in the designated fields.
- Provide your address, including city, state, and zip code, along with your phone number for contact purposes.
- In the section labeled 'I hereby authorize UMHS to release my medical records from:', specify the name of the patient and select the entities from which you want records released.
- Next, indicate who will receive this information by filling out their name, phone number, and address in the appropriate fields.
- Select which specific information you wish to be released by checking the relevant boxes for items like progress notes or discharge summaries.
- Specify the dates of treatment for which records are being requested by filling in the 'From' and 'To' fields.
- Complete any additional sections regarding sensitive information releases as necessary by checking 'Yes' or 'No'.
- Finally, sign and date the form at the bottom. If signed by a legal representative, include their authority description.
Start using our platform today to easily fill out your authorization form for free!
Fill out authorization to release medical records form online
It's free
It's free
See more authorization to release medical records form versions
We've got more versions of the authorization to release medical records form form. Select the right authorization to release medical records form version from the list and start editing it straight away!
| Versions | Form popularity | Fillable & printable |
|---|---|---|
| 2009 | 4.8 Satisfied (287 Votes) |
Got questions?
We have answers to the most popular questions from our customers. If you can't find an answer to your question, please contact us.
Contact us
What is authorization for release of medical records HIPAA compliant?
A Privacy Rule Authorization is an individuals signed permission to allow a covered entity to use or disclose the individuals protected health information (PHI) that is described in the Authorization for the purpose(s) and to the recipient(s) stated in the Authorization.
When HIPAA requires authorization to disclose information, the authorization must what?
The scenarios in which a valid HIPAA authorization form is required are listed in 164.508 and include: Prior to disclosing PHI for marketing purposes. Prior to disclosing PHI for fundraising purposes. Prior to disclosing PHI to a research organization. Prior to disclosing PHI in psychotherapy notes.
What is the DD form for medical records release?
Authorization for Disclosure of Medical or Dental Information (DD Form 2870) Use this form to authorize an individual to release information that is protected under the Federal Privacy Act. This form is not valid to designate a representative for the Appeals process.
How do you allow someone access to your medical records?
A HIPAA Authorization Form is a document that allows a medical provider to share specific health information with another person or group. This can be a doctor, a hospital, or a health care provider, as well as lawyers, mental health professionals, or another similar professional.
Should I accept or decline HIPAA authorization?
Textbook Expert-Verified⬈(opens in a new tab) The correct answer is B. Under HIPAA, when authorization is required to disclose health information, it must include specific core elements defined by the law.
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


People also ask
What must an authorization be under HIPAA?
All authorizations must be in plain language, and contain specific information regarding the information to be disclosed or used, the person(s) disclosing and receiving the information, expiration, right to revoke in writing, and other data.
How to write an authorization to release medical records?
I, the undersigned, authorize the release of, or request access to the information specified below from the medical record(s) of the above name patient. I understand that my records are confidential and cannot be disclosed without my written authorization, except when otherwise permitted by law.