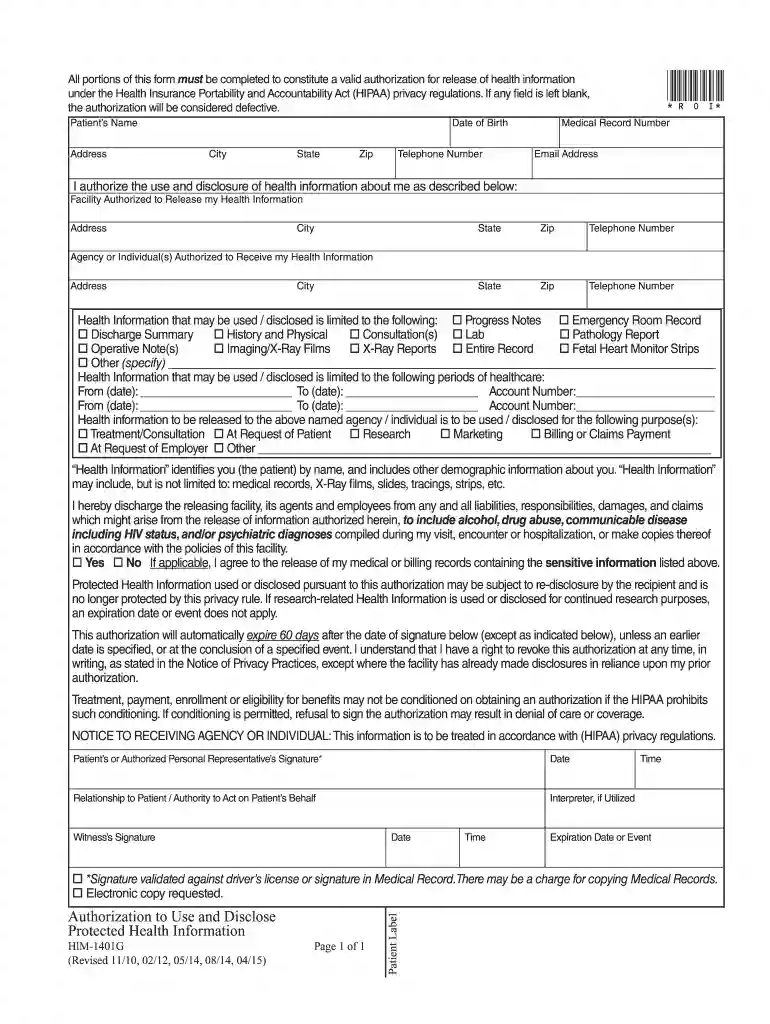
authorization use disclose protected Preview on Page 1

Authorization use disclose protected 2026

Here's how it works

  • 01. Edit your form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
  • 03. Share your form with others

    Send it via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out authorization use disclose protected with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open it in the editor.
  2. Begin by entering the Patient’s Name, Address, Date of Birth, City, State, Zip, and Telephone Number. Ensure all fields are filled out completely to avoid any issues with the authorization.
  3. Next, provide the Medical Record Number and Email Address for further communication regarding your health information.
  4. Identify the Facility Authorized to Release your Health Information by filling in their Address, City, State, Zip, and Telephone Number.
  5. Specify the Agency or Individual(s) Authorized to Receive your Health Information along with their contact details.
  6. Select the specific Health Information that may be used or disclosed from the provided options. You can also specify any other information if needed.
  7. Indicate the periods of healthcare for which this authorization applies by filling in the From and To dates along with Account Numbers if applicable.
  8. Choose the purpose(s) for which your health information will be used or disclosed from the list provided.
  9. Sign and date at the bottom of the form. If applicable, include your relationship to the patient or authority to act on their behalf.

Start using our platform today for free to complete your authorization form effortlessly!

See more authorization use disclose protected versions

We've got more versions of the authorization use disclose protected form. Select the right authorization use disclose protected version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20154.8 Satisfied (93 Votes)

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

Related links

AUTHORIZATION TO DISCLOSE PROTECTED HEALTH

The authorization provided by use of the form means that the organization, entity or person authorized can disclose, commu- nicate, or send the namedRead more

Learn more
notice of privacy practices effective 4/12/2019

Apr 12, 2019 If you revoke your authorization, Inogen will no longer use or disclose your protected health and personal information on file for the reasonsRead more

Learn more
45 CFR 164.508 - Uses and disclosures for which an

A covered entity must obtain an authorization for any use or disclosure of protected health information for marketing.Read more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here