cobra benefits termination form Preview on Page 1

Cobra termination form 2026

Here's how it works

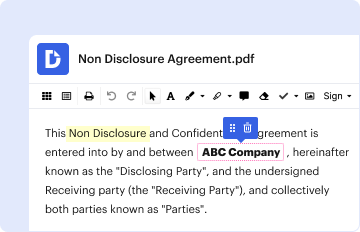
  • 01. Edit your cobra benefits termination form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

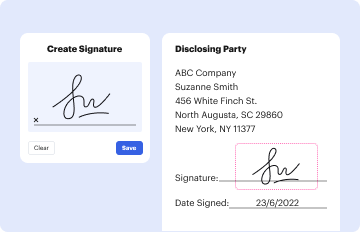
  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
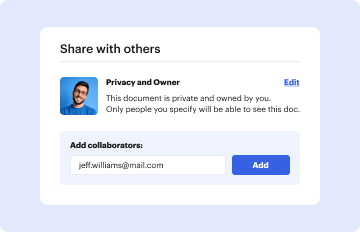
  • 03. Share your form with others

    Send wex cancel cobra via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out cobra termination form with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the COBRA Benefits Termination Form in the editor.
  2. Begin by filling out the Primary Qualified Beneficiary Information. Enter your full name, Social Security Number, and previous employer's name without abbreviations. Provide a day telephone number and an email address for communication.
  3. In the Benefit Termination Information section, specify which benefits you wish to discontinue (Medical, Dental, Vision, etc.). Indicate the effective date of termination using the format mm/dd/yyyy and list all affected individuals.
  4. Complete the Primary Qualified Beneficiary Certification by signing and dating where indicated. If terminating coverage for a spouse, ensure their signature is also included.

Start using our platform today to easily complete your COBRA termination form for free!

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

be ready to get more

Complete this form in 5 minutes or less

wex health cancel cobra

Employee Enrollment Application / Change Request Form

If you selected COBRA or Cal-COBRA as the application reason above, please select one of the following qualifying events: Continuation qualifying event dateRead more

Learn more
COBRA Continuation Coverage

Explore COBRA continuation coverage options, eligibility, and benefits for workers, families, and advisers under HIPAA regulations.

Learn more
TERMINATION

I WISH TO TERMINATE ONLY THE SPOUSE/DEPENDENT(S) LISTED BELOW. TERMINATION DATE. ❑ DEPENDENT. ❑ DIVORCE ❑ ELIGIBLE ❑ DEPENDENT ❑ SUBSCRIBER. OTHER.Read more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here