





Here's how it works
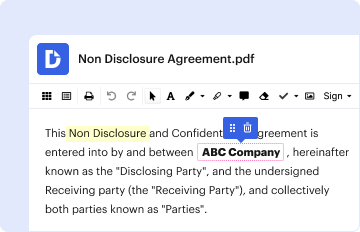
01. Edit your receipt of medical records form online
Type text, add images, blackout confidential details, add comments, highlights and more.
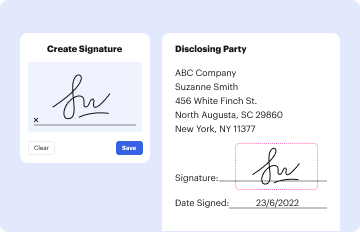
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
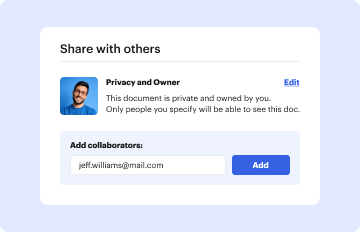
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out Patient Name: Medical Record #: ACKNOWLEDGEMENT OF RECEIPT OF NOTICE OF PRIVACY PRACTICES

- Click ‘Get Form’ to open it in the editor.
- In the 'Patient Name' field, enter your full name as it appears on your medical records.
- Next, fill in the 'Medical Record #' field with your unique medical record number provided by NorthEast Medical Center.
- Read through the Acknowledgement section carefully to understand your rights regarding the Notice of Privacy Practices.
- Sign below the Acknowledgement statement to confirm that you have received a copy of the Notice.
- Fill in your relationship to the patient if you are signing on their behalf, and enter today's date.
- If applicable, complete any additional sections regarding refusal to sign or other notes as necessary.
Start using our platform today for free to easily complete and manage your documents!
Fill out Patient Name: Medical Record #: ACKNOWLEDGEMENT OF RECEIPT OF NOTICE OF PRIVACY PRACTICES By signing below, you acknowledge that you received a copy of the Notice of Privacy Practices for NorthEast Medical Center and other health care online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


