sutter health release of information form Preview on Page 1

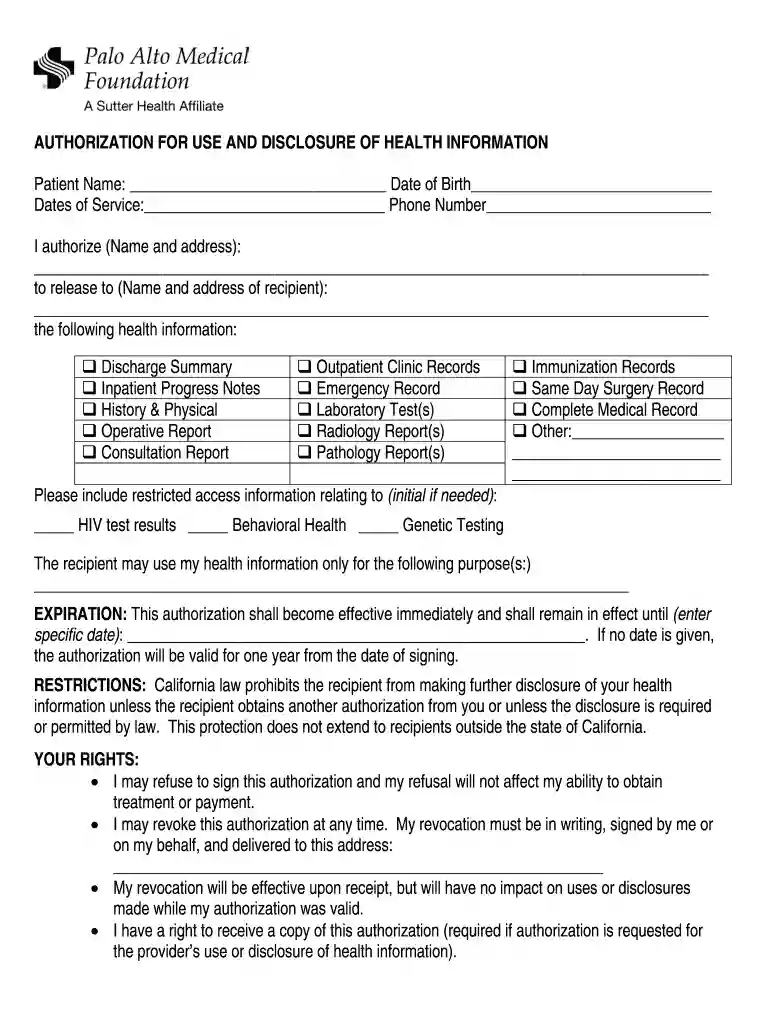
AUTHORIZATION FOR USE AND DISCLOSURE OF HEALTH INFORMATION. Release of Information for the Palo Alto Medical Foundation 2026

Here's how it works

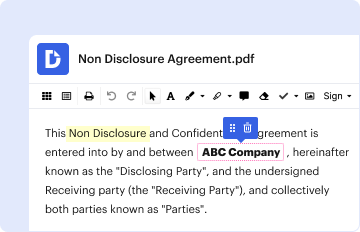
  • 01. Edit your sutter health release of information form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

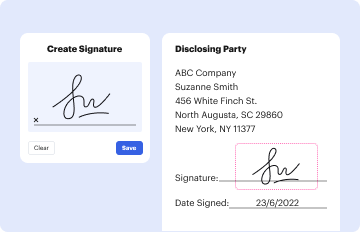
  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
  • 03. Share your form with others

    Send sutter health medical records address via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out AUTHORIZATION FOR USE AND DISCLOSURE OF HEALTH INFORMATION. Release of Information for the Palo Alto Medical Foundation with DocHub

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open it in the editor.
  2. Begin by entering your full name and date of birth in the designated fields at the top of the form.
  3. Fill in the dates of service and your phone number to provide context for your request.
  4. In the section labeled 'I authorize,' write the name and address of the entity you are authorizing to release your health information.
  5. Next, specify who will receive this information by filling out their name and address in the recipient section.
  6. Select which specific health information you wish to disclose by checking the appropriate boxes provided.
  7. If applicable, indicate any restricted access information that should be included by initialing next to those options.
  8. Clearly state the purpose for which your health information may be used in the designated area.
  9. Set an expiration date for this authorization; if left blank, it will remain valid for one year from signing.
  10. Finally, sign and date the form at the bottom, ensuring all required fields are completed before submission.

Start using our platform today to easily complete your authorization form online for free!

See more sutter health release of information form versions

We've got more versions of the sutter health release of information form form. Select the right sutter health release of information form version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20114.9 Satisfied (42 Votes)

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

sutter health prior authorization form

Robert Reiser, Ph

THIS NOTICE DESCRIBES HOW MEDICAL INFORMATION ABOUT YOU MAY BE USED AND. DISCLOSED AND HOW YOU CAN GET ACCESS TO THIS INFORMATION. PLEASE REVIEW IT. CAREFULLY.Read more

Learn more
request for and authorization to release health information

All relevant medical record information needed for court supervision. VA Palo Alto Health Care System. 3801 Miranda Ave. Palo Alto, CA 94304. Santa CruzRead more

Learn more
LIBRARY HIS

Each 128 Family board provides reliable, real-time digital video for machine vision inspection, teleconferencing, medical imaging, surveillance, and many otherRead more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here