AUTHORIZATION FORM - St Luke's Medical Center Preview on Page 1

AUTHORIZATION FORM - St Luke's Medical Center 2026

Here's how it works

  • 01. Edit your form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

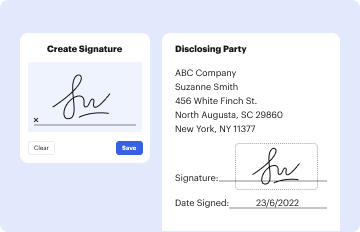
  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
  • 03. Share your form with others

    Send it via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out AUTHORIZATION FORM - St Luke's Medical Center with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the AUTHORIZATION FORM in the editor.
  2. Begin by entering the Patient Name and Date of Birth (DOB) in the designated fields. Ensure accuracy as this information is crucial for identification.
  3. In the section labeled 'The health information you may release', specify the details of the protected health information you wish to disclose. Be clear and concise.
  4. Next, fill in the details of the person(s) or entity authorized to receive this information. Include their Name, Relationship to Patient, Street Address, City, State, Zip Code, and Phone Number.
  5. If applicable, indicate a term date or event for when this authorization will expire. If no expiration is needed, leave this section blank.
  6. Finally, sign and print your name along with the date at the bottom of the form. This signature confirms your authorization.

Start using our platform today to easily complete your AUTHORIZATION FORM for free!

See more AUTHORIZATION FORM - St Luke's Medical Center versions

We've got more versions of the AUTHORIZATION FORM - St Luke's Medical Center form. Select the right AUTHORIZATION FORM - St Luke's Medical Center version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20124.9 Satisfied (25 Votes)
20114.5 Satisfied (62 Votes)

be ready to get more

Complete this form in 5 minutes or less

Got questions?

We have answers to the most popular questions from our customers. If you can't find an answer to your question, please contact us.

If you are a family member of a deceased patient, you can request information if: You have proof of the patients permission prior to his/her death. It is relevant to your own health, and is requested by your physician. You are the executor of the estate and have included a copy of court papers.
Epic is our electronic medical record system, which allows clinicians to document patient information quickly in various encounters across our health system.
To request a copy of a medical record from a physician, call or write to the physician holding the record. If the physician does not respond to this request within a timely manner, you can file a complaint with the NYS Department of Health, Office of Professional Medical Conduct for Physicians.
Access. Only you or your personal representative has the right to access your records. A health care provider or health plan may send copies of your records to another provider or health plan only as needed for treatment or payment or with your permission.
The NYS Department of Health, however, requires medical doctors to retain records for any adult patients for 6 years. Minor patients are kept for 6 years and until one year after the minor docHubes the age of 18 (whichever is longer). For hospitals, medical records must be kept for six years from the date of discharge.

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

People also ask

Death records are not public records and New York State Public Health law protects their confidential nature. Death records cannot be mailed to a P.O. Box or third-party address unless the applicants signature is docHubd.
A HIPAA authorization form gives covered entities permission to use protected health information for purposes other than treatment, payment, or health care operations.

Related links

Release of Information | Baylor Medicine

A completed and signed Authorization for Release of Protected Health Information form in English or Spanish can be sent to our Release of Medical RecordsRead more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here