




Here's how it works
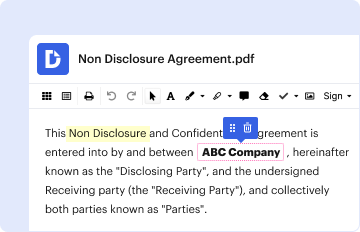
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.
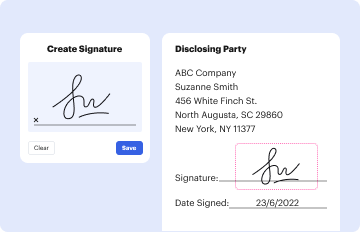
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out Veba Claim Form - Fill Online, Printable, Fillable, BlankDocHub with DocHub

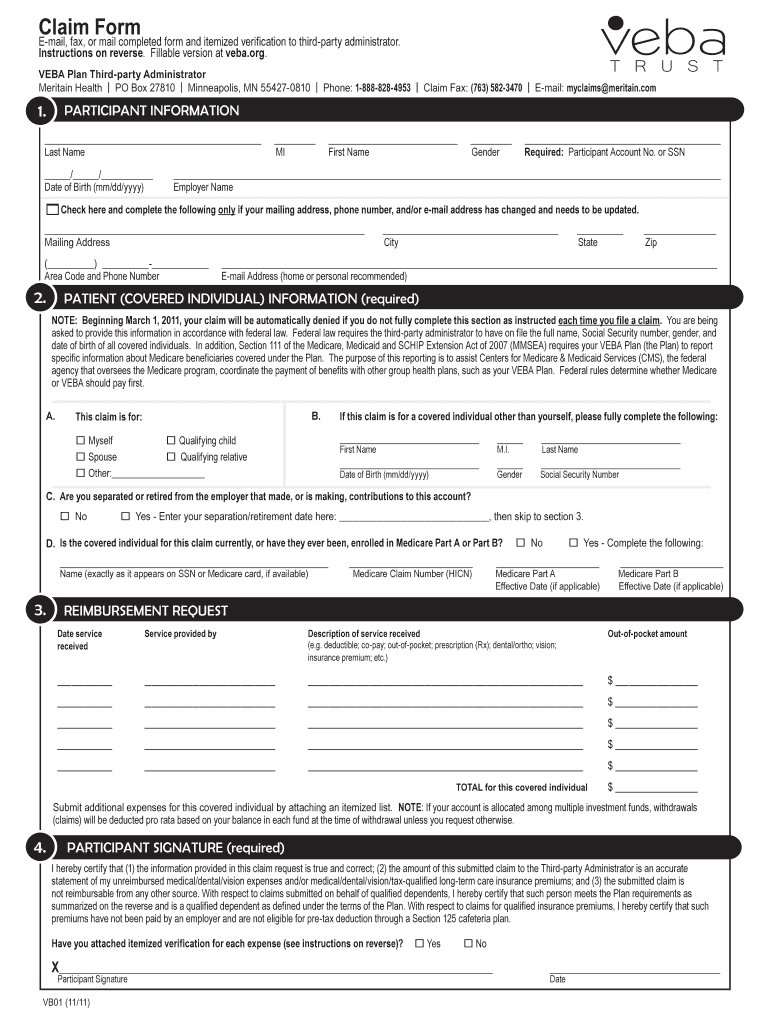
- Click ‘Get Form’ to open it in the editor.
- Begin by filling out the 'Participant Information' section. Enter your last name, first name, date of birth, and gender. Ensure you provide your Participant Account Number or SSN.
- If your contact information has changed, check the box and update your mailing address, phone number, and email address.
- Complete the 'Patient Information' section. Indicate if the claim is for yourself or another covered individual and provide their details including name, date of birth, and Medicare information if applicable.
- In the 'Reimbursement Request' section, list each service received along with the date, provider's name, description of service, and out-of-pocket amount.
- Finally, sign and date the form in the 'Participant Signature' section to certify that all information is accurate.
Start using our platform today to fill out your Veba Claim Form easily and for free!
Fill out Veba Claim Form - Fill Online, Printable, Fillable, BlankDocHub online
It's free
It's free
See more Veba Claim Form - Fill Online, Printable, Fillable, BlankDocHub versions
We've got more versions of the Veba Claim Form - Fill Online, Printable, Fillable, BlankDocHub form. Select the right Veba Claim Form - Fill Online, Printable, Fillable, BlankDocHub version from the list and start editing it straight away!
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


