




Here's how it works
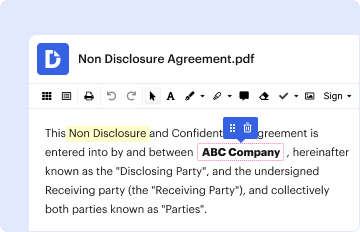
01. Edit your medicaid authorization form online
Type text, add images, blackout confidential details, add comments, highlights and more.
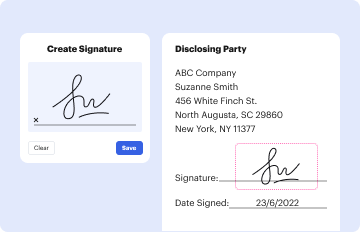
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
03. Share your form with others
Send medicaid authorization form pdf via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out Medicaid Prior Authorization Form with DocHub

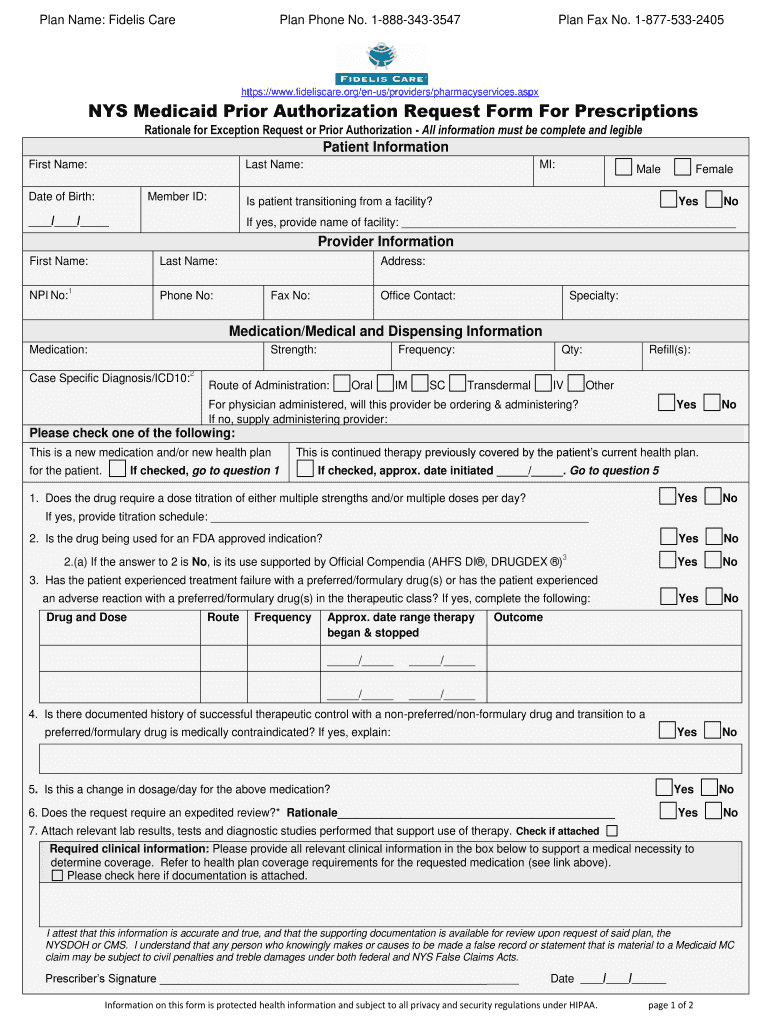
- Click ‘Get Form’ to open the Medicaid Prior Authorization Form in our platform's editor.
- Begin by filling out the Patient Information section. Enter the patient's first name, last name, member ID, date of birth, and gender. If applicable, indicate if the patient is transitioning from a facility.
- Next, complete the Provider Information section. Input your first name, last name, NPI number, phone number, address, fax number, office contact, and specialty.
- In the Medication/Medical and Dispensing Information section, provide details about the medication including its strength, diagnosis code (ICD9), frequency of administration, quantity needed, and refill information.
- Answer all relevant questions regarding dosage titration and previous treatment failures. Ensure to attach any necessary clinical documentation that supports your request.
- Finally, review all entered information for accuracy before signing the form digitally within our editor. Once completed, you can easily export or share it as needed.
Start using our platform today to streamline your Medicaid prior authorization process for free!
Fill out medicaid prior authorization form online
It's free
It's free
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more


