




Here's how it works
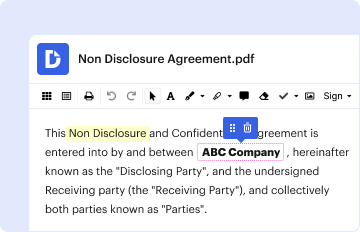
01. Edit your form online
Type text, add images, blackout confidential details, add comments, highlights and more.
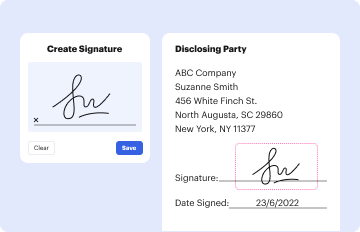
02. Sign it in a few clicks
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
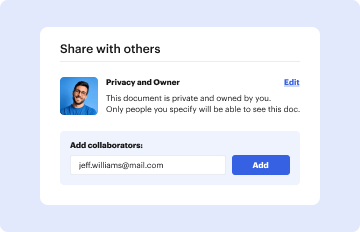
03. Share your form with others
Send it via email, link, or fax. You can also download it, export it or print it out.
How to use or fill out MR 543 02 SPA Patient Authorization for Release of with our platform

- Click ‘Get Form’ to open the MR 543 02 SPA Patient Authorization for Release of in the editor.
- Begin by filling out the 'Patient Information' section. Enter your name, date of birth, medical record number, phone number, and email address.
- In the 'Reason for Request' section, select the appropriate option that describes why you are requesting your medical records.
- Specify the authorized employee or agent from Penn State Health who can discuss your healthcare information by filling in their name.
- Indicate which specific medical information you want included in this disclosure by checking the relevant boxes.
- Complete the 'Addressee Field' with the names and addresses of where to send or receive information.
- Select your preferred format for receiving medical information from the options provided.
- Finally, sign and date the form at the bottom. If someone else is signing on your behalf, include their relationship to you.
Start using our platform today to easily complete your MR 543 02 SPA Patient Authorization for Release of form online for free!
Fill out MR 543 02 SPA Patient Authorization for Release of online
It's free
It's free
See more MR 543 02 SPA Patient Authorization for Release of versions
We've got more versions of the MR 543 02 SPA Patient Authorization for Release of form. Select the right MR 543 02 SPA Patient Authorization for Release of version from the list and start editing it straight away!
Got questions?
We have answers to the most popular questions from our customers. If you can't find an answer to your question, please contact us.
Contact us
What are some authorization requirements to validate release of information?
HIPAA Authorization Defined A description of the PHI. The name of the person making the authorization. The name of the person or organization who is authorized to receive the PHI. A description of the purpose for the use or disclosure. An expiration date for the authorization.
How to fill authorization for release of information?
Begin by specifying your name, the entity authorized to disclose information, and the individuals or entities you authorize to receive it. Indicate the specific information and purpose for which it will be disclosed, add an expiration date or event, and sign and date the form to confirm your consent.
What is an authorization and release form?
A medical authorization release form is a form that provides insurance companies with the authority to delve into your medical records. After receiving a claim, insurance companies must review the injuries outlined in the claim to come to their own valuation.
Do you have to fill out a release of information form?
To respect HIPAA compliance rules, a signed HIPAA release form must be obtained from a patient before their protected health information can be shared with other individuals or organizations, except in the case of routine disclosures for treatment, payment or healthcare operations permitted by the HIPAA Privacy Rule.
Security and compliance
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Learn more




