ps 452 Preview on Page 1

EMPLOYEE BENEFITS DIVISION Eligibility for a Waiver of Empire 2026

Here's how it works

  • 01. Edit your ps 452 online

    Type text, add images, blackout confidential details, add comments, highlights and more.

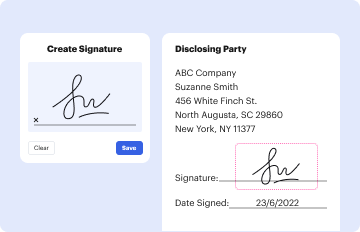
  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
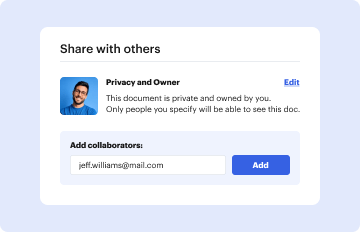
  • 03. Share your form with others

    Send ps452 via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out EMPLOYEE BENEFITS DIVISION Eligibility for a Waiver of Empire with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the EMPLOYEE BENEFITS DIVISION Eligibility for a Waiver of Empire in the editor.
  2. Begin by completing the Enrollee Portion. Fill in your Last Name, First Name, Middle Initial, Date of Birth, and Empire Plan ID Number. Provide your Home Address and Telephone Number.
  3. Indicate whether this is your first waiver or an additional waiver related to your sickness/injury by checking the appropriate box.
  4. Once you have completed your section, print pages 2 and 3 and provide them to your treating physician for completion.
  5. After the physician fills out their portion on page 3, ensure they send all pages back to UnitedHealthcare at the specified address.
  6. Keep a copy of the completed form for your records before submission.

Start using our platform today to easily complete your application for a waiver!

See more ps 452 versions

We've got more versions of the ps 452 form. Select the right ps 452 version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20204.2 Satisfied (60 Votes)
20064 Satisfied (53 Votes)

be ready to get more

Complete this form in 5 minutes or less

Got questions?

We have answers to the most popular questions from our customers. If you can't find an answer to your question, please contact us.

Toll free: 1-877-7-NYSHIP (1-877-769-7447) See pages 10 and 11 for additional information. See page 12 for a complete list. Call about retirement checks and retirement system benefits.
NYSHIP offers a waiver of Healthcare premium for up to 12 months due to a total disability. There is a required application, PS-452, Application for Waiver of Premium.
Cost. The average waiver of premium can typically add $10 to $50 per month to a policys cost. That amount can vary based on your age, health, and coverage amount.
An insurance company may offer an enhanced waiver of premium for payer rider options. For example, a company might provide a potential policyholder an opportunity to expand the waiver to cover unemployment or possibly skip payments in the event a policyholder is laid off and out of work.
Waiver of Premium Waives Disability insurance premium for employees who become totally disabled and are no longer able to work. Survivor Benefit Pays a monthly benefit or a lump sum in the event of a disabled employees death. A three-month lump sum is standard.

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

People also ask

The Empire Plan is NYSHIPs unique health insurance plan designed exclusively for New York States public employees and employers. The Empire Plan pays for covered hospital services, physicians bills, prescription drugs and other medical expenses.

ny ps 452

Empire-Plan-2024-at-a-glance.pdf by A AT

by A AT 2024 Cited by 2 In order to receive maximum benefits under the Plan, you must follow the Benefits Management Program requirements. This includes obtaining.

Learn more
EMPLOYEE BENEFITS DIVISION Eligibility for a Waiver of

To qualify for a waiver of your Empire Plan premium, you must meet all four of the following requirements: 1. You are currently enrolled in The Empire Plan;. 2.

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here