highmark form Preview on Page 1

Highmark form 2026

Here's how it works

  • 01. Edit your highmark form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

  • 02. Sign it in a few clicks

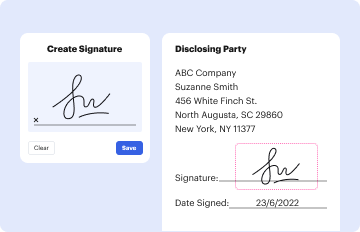
    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
  • 03. Share your form with others

    Send medication request form via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out highmark form with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the highmark form in the editor.
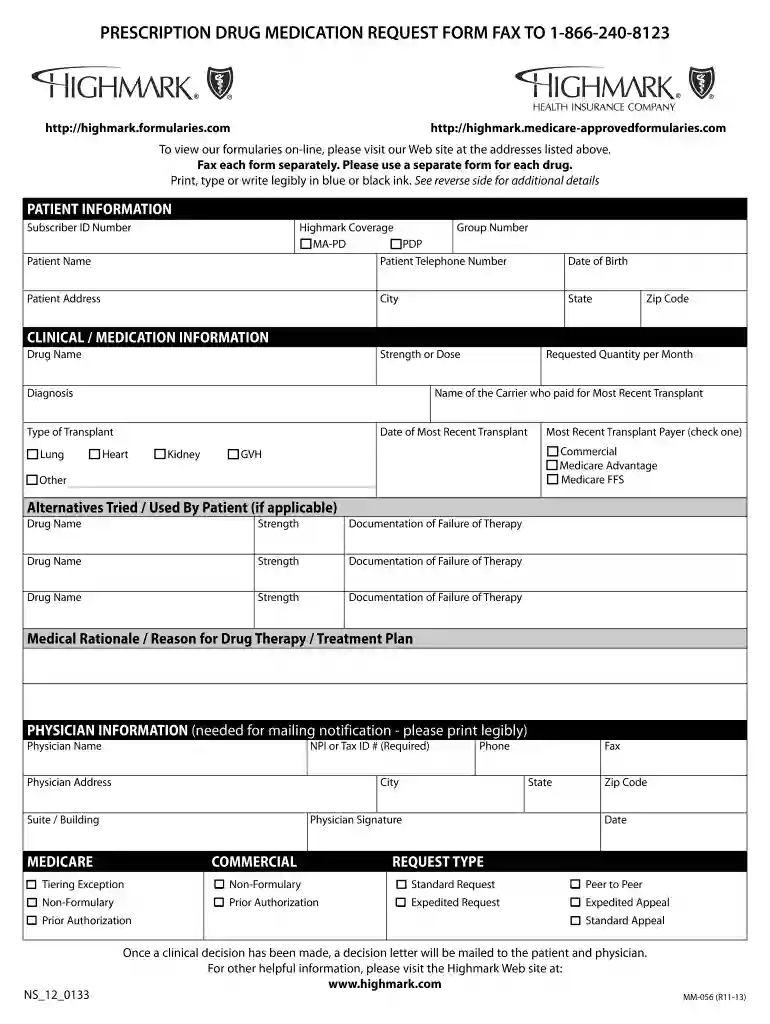
  2. Begin by filling out the 'Patient Information' section. Enter the Subscriber ID Number, Group Number, Patient Name, Address, Date of Birth, and Telephone Number. Ensure all details are accurate and legible.
  3. Next, move to the 'Clinical / Medication Information' section. Specify the Drug Name, Strength or Dose, Diagnosis, and any relevant transplant information if applicable. Be sure to document any alternatives tried by the patient.
  4. Proceed to complete the 'Physician Information' section. Provide the Physician's Name, NPI or Tax ID number, Address, Phone number, and Signature. This information is crucial for mailing notifications.
  5. Finally, select your 'Request Type' from options such as Peer to Peer or Expedited Appeal. Review all entries for accuracy before submitting.

Start using our platform today for free to streamline your highmark form completion!

See more highmark form versions

We've got more versions of the highmark form form. Select the right highmark form version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20134.8 Satisfied (236 Votes)

be ready to get more

Complete this form in 5 minutes or less

Got questions?

We have answers to the most popular questions from our customers. If you can't find an answer to your question, please contact us.

This form is used to authorize Blue Cross to release your protected health information (PHI) to another person or entity.
The Highmark BCBS Overpayment Form is a standardized document used by healthcare providers, patients, or billing entities to notify Highmark BCBS of an overpayment related to a specific claim or series of claims.
Go to .highmarkblueshield.com and click on Register Now. Fill out the information needed to register. If you do not have your member ID card, use your Social Security number. Highmark will require you to enter a 4 digit PIN into our website before you can see any personal information.

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

highmark form pdf

COORDINATION OF BENEFITS QUESTIONNAIRE

A. Within the past year, have you or any member of your family been covered by another insurance company? q No. q Yes. Please complete the remainder of thisRead more

Learn more
Highmark BCBS HIPAA Authorization Form.pdf

I COMPLETE THE HIGHMARK AUTHORIZATION FOR DISCLOSURE OF HEALTH INFORMATION (ADHI) FORM? Section 1: 1. Identify who will be disclosing the information.

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here