


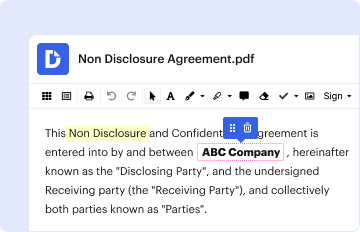
01. Edit your illinois prior authorization form online
Type text, add images, blackout confidential details, add comments, highlights and more.


Type text, add images, blackout confidential details, add comments, highlights and more.
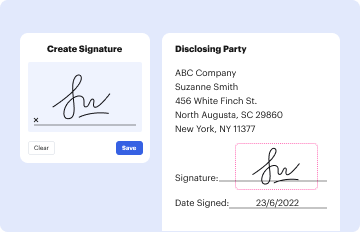
Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
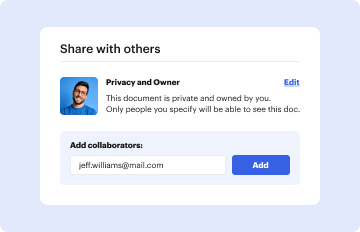
Send illinois prior authorization via email, link, or fax. You can also download it, export it or print it out.

Start using our platform today to fill out your Illinois Prior Authorization Form quickly and efficiently!
We've got more versions of the illinois prior authorization form form. Select the right illinois prior authorization form version from the list and start editing it straight away!
At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.
Patient Information. Name: Last. First. (MI) . Date of Birth: / /. University of Chicago MRN (if applicable):. Gender: Male. Female.
Illinois Medicaid Pharmacy Prior Authorization Request Form. State of Illinois. Department of Healthcare and Family Services. Fax completed form to patients
Prior Authorization Request Form, is available in the Healthcare Services section of this. 13. Page 14. Manual. Physician administered drugs require the


