verication form for providers Preview on Page 1

Verication form for providers 2026

Here's how it works

  • 01. Edit your form online

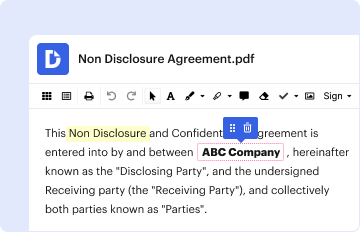
    Type text, add images, blackout confidential details, add comments, highlights and more.

  • 02. Sign it in a few clicks

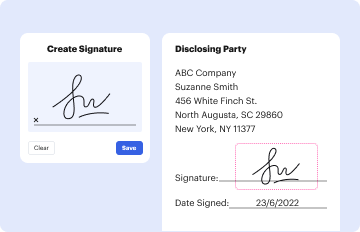
    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
  • 03. Share your form with others

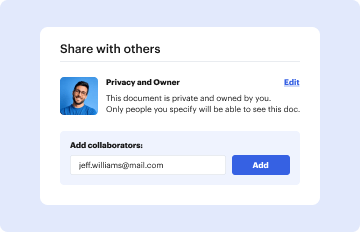
    Send it via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out the verification form for providers with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open it in the editor.
  2. Begin by filling out the 'Prescriber Instructions' section. Indicate the services requested and select the site of service from the provided options.
  3. In the 'Physician/Facility Information' section, enter your details including physician name, facility name, address, and contact information. Ensure all fields are completed accurately.
  4. Next, provide 'CUBICIN Prescription Information'. Fill in dates of service, patient weight, number of vials requested, and dosing information.
  5. Complete the 'Patient Information' section with details such as date of birth and address. If applicable, check if the patient is a US resident.
  6. In the 'Insurance Information' section, attach copies of insurance cards if available. Fill in primary and secondary insurance details as required.
  7. If applying for Patient Assistance Program, complete the financial information section and indicate whether you can be contacted.
  8. Finally, ensure that all required signatures are obtained from both patient and physician before submitting.

Start using our platform today to streamline your document editing and form completion process for free!

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

Related links

Forms - New York State of Health

The Authorized Representative Identity Verification Form serves as a tool for designating someone to act on your behalf. providers. Any informationRead more

Learn more
ROC Reporting Instructions

by PCI PCI 2011 Cited by 3 Providers for PCI DSS assessments of shared hosting providers, to verify that shared hosting providers protect their entities (merchants and service providers).Read more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here