(FSA) Claim Form - myuhc Preview on Page 1

(FSA) Claim Form - myuhc 2026

Here's how it works

  • 01. Edit your form online

    Type text, add images, blackout confidential details, add comments, highlights and more.

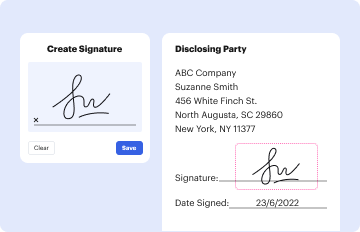
  • 02. Sign it in a few clicks

    Draw your signature, type it, upload its image, or use your mobile device as a signature pad.
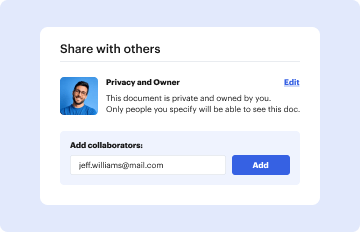
  • 03. Share your form with others

    Send it via email, link, or fax. You can also download it, export it or print it out.

How to use or fill out (FSA) Claim Form - myuhc with our platform

Form edit decoration
9.5
Ease of Setup
DocHub User Ratings on G2
9.0
Ease of Use
DocHub User Ratings on G2
  1. Click ‘Get Form’ to open the (FSA) Claim Form - myuhc in the editor.
  2. Begin by filling out the Employee Information section. Enter your employer's name, daytime phone number, and your personal details including your name, SSN, home address, and email address.
  3. In the Health Care Account section, list each eligible expense. For each entry, provide the patient’s name, relationship to you, date(s) of service, service provided, and the eligible reimbursement amount. Ensure you attach necessary documentation like EOBs or bills.
  4. For the Dependent Care Account section, include dependent details such as their name and birthdate. Attach a statement from your care provider that includes their information and signature.
  5. Review all entries for accuracy before signing and dating the form at the bottom. Make sure to keep a copy for your records.

Start using our platform today to easily complete your (FSA) Claim Form - myuhc for free!

See more (FSA) Claim Form - myuhc versions

We've got more versions of the (FSA) Claim Form - myuhc form. Select the right (FSA) Claim Form - myuhc version from the list and start editing it straight away!

VersionsForm popularityFillable & printable
20174.6 Satisfied (51 Votes)
20094 Satisfied (51 Votes)

be ready to get more

Complete this form in 5 minutes or less

Security and compliance

At DocHub, your data security is our priority. We follow HIPAA, SOC2, GDPR, and other standards, so you can work on your documents with confidence.

Related links

Medical Claim Form

What is this form for? This form is for out-of-network claims ONLY, to ask for payment for eligible health care you have received.Read more

Learn more
Dependent Care Claim Form

FLEXIBLE SPENDING ACCOUNT. (FSA) Dependent Care Claim Form. UnitedHealthcare. A UnitedHealth Group Company. MAIL CLAIM FORM TO: Health Care Account ServiceRead more

Learn more
If you believe that this page should be taken down, please follow our DMCA take down process here